
Last updated on
Nov 12, 2014

Get the free Authorization for Disclosure of Information
We are not affiliated with any brand or entity on this form
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Disclosure Authorization
The Authorization for Disclosure of Information is a healthcare form used by patients and guardians to authorize the release of medical information to the Medical Employability Program.
pdfFiller scores top ratings on review platforms




Who needs Disclosure Authorization?
Explore how professionals across industries use pdfFiller.

Disclosure Authorization is needed by:
-
Patients seeking to authorize medical record disclosure
-
Parents or guardians acting on behalf of patients
-
Employees participating in the Medical Employability Program
-
Medical providers releasing patient information
-
Legal representatives handling medical consent
Comprehensive Guide to Disclosure Authorization
What is the Authorization for Disclosure of Information?
The Authorization for Disclosure of Information is a pivotal healthcare form in the United States, designed to facilitate the release of medical information from healthcare providers. This authorization is essential for patients seeking to transfer their medical records to the Medical Employability Program of the Federal Occupational Health. Governed by the Privacy Act of 1974, this form ensures compliance with federal regulations surrounding medical information disclosure.
Key parties involved in this process include the patient, the healthcare provider, and the Medical Employability Program. Understanding the roles of these parties is crucial for a smooth information exchange while safeguarding patient privacy.
Purpose and Benefits of the Authorization for Disclosure of Information
This authorization plays a vital role in enabling patients to access their medical records timely. By using this form, patients ensure that their medical information is shared securely with relevant parties, thus supporting their participation in programs like the Medical Employability Program. Obtaining patient consent not only protects individual privacy but also strengthens trust between patients and healthcare providers.
The benefits of ensuring informed consent extend beyond legal compliance; they enhance the integrity of the healthcare process and improve communication among patients, providers, and programs involved in patient care.
Key Features of the Authorization for Disclosure of Information
The Authorization for Disclosure of Information includes several essential fields that must be completed accurately. These fields typically include:
-
Employee information
-
Purpose for disclosure
-
Patient details, including name and date of birth
-
Last four digits of the Social Security Number (SSN)
Additionally, the form necessitates multiple signatures, which may include those of the patient and a parent, guardian, or power of attorney. Importantly, the authorization remains valid for six months from the date of signing, which ensures that users understand the timeline for information sharing.
Who Needs the Authorization for Disclosure of Information?
Anyone wishing to release their medical records should understand their rights as a patient. This includes not only the patient themselves but also parents, guardians, or individuals holding power of attorney. These representatives must be properly identified in the authorization form to validate the disclosure of medical details.
Specific scenarios often call for this authorization, such as transitioning medical care providers or applying for disability benefits. Understanding these conditions helps ensure compliance and appropriate handling of sensitive information.
How to Fill Out the Authorization for Disclosure of Information Online (Step-by-Step)
Completing the Authorization for Disclosure of Information online is straightforward if you follow these steps:
-
Access the online form on the designated platform.
-
Enter the required employee information accurately, including their name and agency.
-
Specify the purpose of the disclosure to inform relevant parties.
-
Provide patient details, such as name, date of birth, and last four SSN digits.
-
Review all information for accuracy and completeness before submission.
Each step requires careful attention to detail, as errors can delay the authorization process.
Common Errors and How to Avoid Them When Filling Out the Authorization
While completing the Authorization for Disclosure of Information, users may encounter several frequent errors. Common issues include:
-
Missing signatures from the necessary parties
-
Incomplete or incorrect patient information
-
Failure to specify the purpose for disclosure
To avoid these pitfalls, users should consider using validation checklists to ensure every required field is filled out accurately before finalizing the form.
How to Sign or Notarize the Authorization for Disclosure of Information
Understanding the signing requirements for the Authorization for Disclosure of Information is crucial for validation. There are key differences between digital and wet signatures, which are important to note. Digital signatures provide a convenient and secure method of signing online forms, while wet signatures may require notarization if specified by certain healthcare providers or jurisdictions.
If notarization is needed, the process typically involves presenting identification and signing the form in the presence of a notary public. This step is important, as it affirms the authenticity of the signatures and the intent behind the authorization.
Submission Methods and Where to Submit the Authorization for Disclosure of Information
Once the Authorization for Disclosure of Information is completed, it can be submitted through various methods. These options include:
-
Online submission via designated healthcare platforms
-
Mailing the completed form to the appropriate healthcare provider or agency
-
Delivering the form in person to the facility involved
After submission, it is crucial to follow up with the relevant parties to ensure the form has been received and processed appropriately.
Security and Compliance when Handling the Authorization for Disclosure of Information
Handling the Authorization for Disclosure of Information involves stringent security measures to protect sensitive medical information. Compliance with regulations such as HIPAA ensures that data is handled with the utmost care and confidentiality.
The commitment to security includes implementing data protection measures that safeguard patient information throughout the disclosure process. Platforms like pdfFiller adhere to these standards to maintain user trust and confidentiality.
Discover How pdfFiller Can Help You with the Authorization for Disclosure of Information
pdfFiller offers an efficient solution for individuals needing to complete the Authorization for Disclosure of Information. With its user-friendly interface, this platform simplifies the process of filling out and managing healthcare forms. Users can easily eSign documents and securely save their completed forms without the need for downloading software.
Explore additional features within pdfFiller that enhance document management, providing users with a comprehensive tool for handling healthcare documentation.
How to fill out the Disclosure Authorization
-
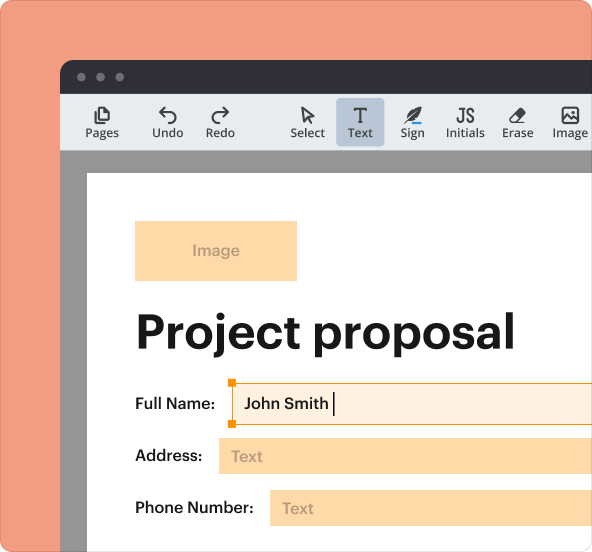
1.To access the Authorization for Disclosure of Information form on pdfFiller, visit the pdfFiller website and search for this specific form in the search bar.
-
2.Once you find the form, click on it to open it in the pdfFiller editor interface. You will see toolbars and fillable fields throughout the document.
-
3.Before starting, gather necessary information such as the patient’s name, date of birth, and last four digits of their Social Security Number, along with details about the agency and purpose of disclosure.
-
4.Start filling in the required fields, such as the employee’s name and agency by clicking on the respective areas. Use pdfFiller's tools to navigate through the form seamlessly.
-
5.Make use of the checkboxes available for various purposes of disclosure as you fill out the form to ensure all applicable sections are completed.
-
6.Once you have completed all required fields, take the time to review the form thoroughly to ensure all information is accurate and complete.
-
7.To finalize, add the signatures of the patient and the guardian or power of attorney by utilizing the 'signature' tool located in the pdfFiller interface.
-
8.After reviewing your form, you can save it, download it as a PDF, or submit it directly through pdfFiller if required by your agency.
Who is eligible to use the Authorization for Disclosure of Information form?
This form is eligible for use by patients who require their medical information to be shared, as well as parents, guardians, or legal representatives acting on behalf of a patient.
What details must I include when completing the form?
You will need to provide the patient’s name, date of birth, the last four digits of their Social Security Number, the name of the employee, the agency, and the purpose for the disclosure.
How do I submit the completed form?
Upon completing the form on pdfFiller, you have several options. You can save the document to your device, download it as a PDF, or submit it directly to your designated agency or program via email.
What common mistakes should I avoid while filling out this form?
Ensure that all required fields are filled accurately and double-check spelling, especially in names and dates. Missing signatures or incorrect Social Security Numbers could delay processing.
How long is the Authorization for Disclosure valid?
The authorization is valid for six months from the date of the signature. Make sure to renew it if you require continued access to medical information beyond this period.
Are notarization or additional documents required?
This specific form does not require notarization. However, ensure you have all personal details ready to provide as supporting documentation may be necessary depending on the agency.
What if I need to change information after submitting the form?
If changes are needed after submission, contact the receiving agency immediately. They will guide you on how to rectify the information or if a new form is necessary.
Related Forms




Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.