
Last updated on
Sep 1, 2026

OH OH-P-1175 free printable template
pdfFiller is not affiliated with any government organization

Fill out
Complete the form online in a simple drag-and-drop editor.

eSign
Add your legally binding signature or send the form for signing.

Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is OH OH-P-1175
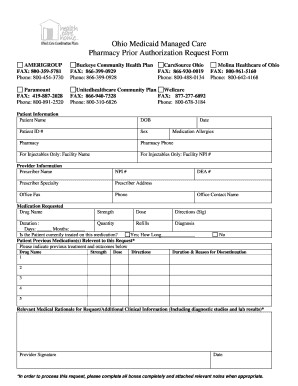
The Ohio Medicaid Managed Care Prior Authorization Request Form is a healthcare document used by providers to request prior authorization for medications or treatments for Medicaid patients.
pdfFiller scores top ratings on review platforms


Who needs OH OH-P-1175?
Explore how professionals across industries use pdfFiller.

OH OH-P-1175 is needed by:
-
Healthcare providers in Ohio
-
Medicaid facilities and institutions
-
Pharmacies handling Medicaid prescriptions
-
Health insurance coordinators
-
Patients seeking medication approval
Comprehensive Guide to OH OH-P-1175
What is the Ohio Medicaid Managed Care Prior Authorization Request Form?
The Ohio Medicaid Managed Care Prior Authorization Request Form is a crucial document used by healthcare providers in Ohio. Its purpose is to request prior authorization for specific medications or treatments that Medicaid patients require. This form plays a significant role in the healthcare system by ensuring that Medicaid patients can access necessary medical services efficiently.
Understanding this form is vital for providers, as it outlines the necessary information for approval and helps streamline the treatment process for patients who depend on Medicaid for their healthcare needs.
Purpose and Benefits of the Ohio Medicaid Managed Care Prior Authorization Request Form
This form is essential in facilitating timely access to medications and treatments that Medicaid patients often need. By submitting a complete and accurate Ohio Medicaid Managed Care Prior Authorization Request Form, providers can expedite the review process for treatment approval.
Both providers and patients benefit significantly from the effective use of this form, as it enhances communication between healthcare professionals and insurance providers, ultimately leading to improved patient care.
Key Features of the Ohio Medicaid Managed Care Prior Authorization Request Form
The Ohio Medicaid Managed Care Prior Authorization Request Form includes several fillable fields that are necessary for processing the request. Key fields include:
-
Patient Name
-
Drug Name
-
Provider Signature
-
Diagnosis
-
Directions
Completing all fields accurately is crucial for approval, as missing or incorrect information can lead to delays or denials in authorization.
Who Needs the Ohio Medicaid Managed Care Prior Authorization Request Form?
Healthcare providers are the primary users of the Ohio Medicaid Managed Care Prior Authorization Request Form. It is especially relevant for Medicaid patients who require prior authorization for their medications or treatments. Understanding who needs this form helps improve the efficiency of the authorization process.
How to Fill Out the Ohio Medicaid Managed Care Prior Authorization Request Form Online (Step-by-Step)
To fill out the Ohio Medicaid Managed Care Prior Authorization Request Form using pdfFiller, follow these steps:
-
Access the form on the pdfFiller platform.
-
Enter the required patient information, such as name and ID number.
-
Input medication details, including drug name and dosage.
-
Gather necessary signatures from the provider.
-
Review the completed form for accuracy before submission.
Pay close attention to common pitfalls, such as leaving fields blank or providing incorrect information, as these can hinder the approval process.
Required Documents and Supporting Materials
When submitting the Ohio Medicaid Managed Care Prior Authorization Request Form, it is important to include essential documentation to support your request. Some of the required materials may include:
-
Medical history of the patient
-
Supporting letters from specialists
-
Prescription information
A pre-filing checklist can help ensure that all necessary documents are gathered before submission to avoid delays.
Submission Methods and Delivery for the Ohio Medicaid Managed Care Prior Authorization Request Form
Providers have several options for submitting the Ohio Medicaid Managed Care Prior Authorization Request Form, including:
-
Online submission through secure portals
-
Mailing the completed form to the appropriate address
-
Faxing the document directly
After submission, it is essential to confirm receipt to ensure the request is being processed without delay.
Common Errors in Completing the Ohio Medicaid Managed Care Prior Authorization Request Form
Completing the Ohio Medicaid Managed Care Prior Authorization Request Form correctly is crucial for ensuring approval. Common errors include:
-
Missing information in fillable fields
-
Incorrect signatures or not signing at all
A validation checklist can help users review their form before submission, reducing the likelihood of mistakes.
Privacy and Data Protection for the Ohio Medicaid Managed Care Prior Authorization Request Form
Confidentiality is paramount when submitting sensitive patient information through the Ohio Medicaid Managed Care Prior Authorization Request Form. Ensuring the security of this data protects patients' privacy and complies with regulations. pdfFiller implements robust security measures, including 256-bit encryption and compliance with SOC 2 Type II standards, to safeguard users' information.
Streamline Your Process with pdfFiller
Utilizing pdfFiller's features can greatly enhance the experience of completing and submitting the Ohio Medicaid Managed Care Prior Authorization Request Form. With capabilities to edit, fill, and eSign securely, users can streamline their documentation processes efficiently.
pdfFiller's intuitive platform ensures user-friendliness while maintaining high-security standards, making it a reliable choice for handling sensitive documents.
How to fill out the OH OH-P-1175
-
1.Access the Ohio Medicaid Managed Care Prior Authorization Request Form on pdfFiller by searching its name in the platform’s search bar.
-
2.Once found, open the form to see fillable fields displayed clearly. Hover over each field for additional instructions if needed.
-
3.Before you begin completing the form, gather essential information such as the patient's name, date of birth, and ID number along with the prescriber’s details.
-
4.Continue by filling in all required fields, including the Drug Name, Strength, Dose, Directions, Duration, Quantity, and any previous medications used.
-
5.Ensure each box is completely and accurately filled out as per the detailed instructions to avoid delays.
-
6.Once you have filled in all relevant sections, review the information carefully for accuracy and completeness.
-
7.Check that the provider's signature is included in the designated area.
-
8.To finalize your form, save your progress, and consider downloading a copy for your records or to submit separately.
-
9.To submit through pdfFiller, choose the option to send via email or directly to the designated Medicaid office using the provided submission method.

Who is eligible to use the Ohio Medicaid Managed Care Prior Authorization Request Form?
The form is specifically for healthcare providers in Ohio that require prior authorization for medications or treatments for Medicaid patients. Providers must ensure they meet all guidelines set forth by Ohio Medicaid to be eligible.
What supporting documents are required with the form submission?
Providers should attach relevant medical documentation that justifies the authorization request. This may include previous medication records, physician notes, and any additional information supporting the medical necessity of the requested treatment.
What are common mistakes to avoid when filling out this form?
Inaccurate patient or provider information, incomplete fields, or lack of required signatures can lead to processing delays. Ensure all boxes are filled out and double-check for mistakes before submission.
How do I submit the completed form?
The completed Ohio Medicaid Managed Care Prior Authorization Request Form can be submitted electronically through pdfFiller or printed and sent via mail or fax to the appropriate Medicaid office as per the instructions provided.
Are there deadlines to submit this form?
It's essential to verify specific deadlines for submission to ensure timely processing. Typically, authorization requests are expected to be submitted as soon as the need arises to avoid treatment delays.
What is the processing time for authorization requests?
Processing times may vary, but providers can generally expect a response within a few days to a week. For urgent requests, ensure to indicate the urgency on the form.
Can I amend a submitted form if additional information is needed?
Yes, if additional information is required after submission, you should contact the Medicaid office directly to understand the amendment process and provide any missing details promptly.

If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.