
Last updated on
Oct 23, 2026

Humana Military Patient Referral Authorization Form free printable template
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Humana Military Patient Referral Authorization Form
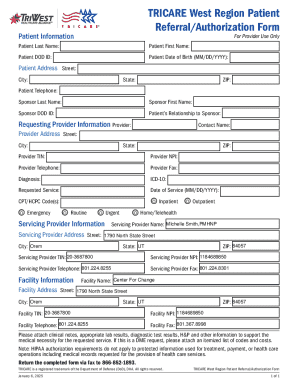
The Patient Referral Authorization Form is a healthcare document used by patients to request authorization for medical services under TRICARE.
pdfFiller scores top ratings on review platforms




Who needs Humana Military Patient Referral Authorization Form?
Explore how professionals across industries use pdfFiller.

Humana Military Patient Referral Authorization Form is needed by:
-
TRICARE beneficiaries requiring medical referrals
-
Healthcare providers submitting referral requests
-
Patient advocates assisting with healthcare coordination
-
Insurance administrators verifying medical necessity
-
Healthcare facilities managing patient care transitions
Comprehensive Guide to Humana Military Patient Referral Authorization Form
What is the Patient Referral Authorization Form?
The Patient Referral Authorization Form primarily functions to request authorization for medical services under TRICARE. This form is crucial for TRICARE beneficiaries who seek to access specialized medical care. It requires essential patient information and provider details to ensure a smooth referral process.
Proper completion of the TRICARE referral form is vital as it facilitates prompt and appropriate medical service access while adhering to TRICARE guidelines.
Purpose and Benefits of the Patient Referral Authorization Form
The primary purpose of the Patient Referral Authorization Form is to streamline the healthcare referral process, enabling healthcare providers to request necessary services efficiently. Utilizing this patient authorization form offers numerous advantages, including improved turnaround times for referrals and ensuring compliance with TRICARE protocols.
Additionally, this process enhances the quality of care by ensuring that beneficiaries receive the appropriate medical attention without unnecessary delays.
Who Needs the Patient Referral Authorization Form?
The target audience for the Patient Referral Authorization Form includes both patients needing specialized care and healthcare providers facilitating referrals. This form is necessary in situations like referrals to specialists, where authorization is mandated by TRICARE policy.
It ensures that all involved parties are informed and adhere to the required protocols for obtaining medical services.
Key Features of the Patient Referral Authorization Form
This form includes several essential features, such as sections dedicated to clinical information, diagnosis codes, and other necessary patient and provider information. The fillable sections provide options for various medical services and simplify the completion process.
Moreover, the option for electronic submission significantly enhances user convenience, reducing the time and effort required for submission.
How to Fill Out the Patient Referral Authorization Form Online (Step-by-Step)
Completing the Patient Referral Authorization Form online can be done efficiently by following these steps:
-
Access the fillable form template online.
-
Enter patient information accurately, including name, address, and details of any other health insurance.
-
Provide the provider’s information, including specialty and contact details.
-
Fill out the clinical sections, ensuring diagnosis codes are entered correctly.
-
Review all information for accuracy before submission.
To avoid common mistakes, double-check all entries, especially numerical codes and personal details.
Submission Methods and Delivery of the Patient Referral Authorization Form
The Patient Referral Authorization Form can be submitted through various methods, including online and via fax. After submission, recipients can expect processing times to vary, with confirmation of receipt typically provided by the handling office.
Understanding these expected timelines helps manage patient expectations during the referral process.
Security and Compliance for the Patient Referral Authorization Form
pdfFiller implements strong security measures when handling the Patient Referral Authorization Form, including 256-bit encryption to protect sensitive information. Compliance with HIPAA regulations is critical in safeguarding patients' private data, ensuring that information is secure throughout the submission process.
Maintaining such privacy practices is essential to build trust and provide peace of mind to patients submitting their personal health information.
Common Errors and How to Avoid Them
Users of the Patient Referral Authorization Form often make frequent errors, such as leaving required fields blank or misentering diagnosis codes. To prevent these pitfalls, follow these guidelines:
-
Ensure all mandatory fields are filled out before submission.
-
Double-check the accuracy of information, particularly medical codes and patient identifiers.
Attention to detail during completion will help prevent form rejections and delays in the referral process.
What Happens After You Submit the Patient Referral Authorization Form?
Once the Patient Referral Authorization Form is submitted, patients can track the status of their application and understand the approval process. Awareness of these procedures allows for better communication with healthcare providers regarding referrals.
Additionally, it is advisable to keep copies of submitted forms for personal records, ensuring that patients have documentation of their requests.
Experience the Ease of Using pdfFiller for Your Patient Referral Authorization Form
Using pdfFiller for completing and submitting the Patient Referral Authorization Form offers users a convenient and user-friendly experience. Features such as editing, eSigning, and secure submission make the process straightforward.
pdfFiller provides support for users encountering form-related queries, ensuring assistance is readily available for a smooth workflow.
How to fill out the Humana Military Patient Referral Authorization Form
-
1.Access the Patient Referral Authorization Form on pdfFiller by searching for its name in the template library.
-
2.Open the form and familiarize yourself with the layout, including the required fields and instructions for completion.
-
3.Gather all necessary information before you start, including patient details, other health insurance information, and provider specifics.
-
4.Begin by filling out each blank field with accurate patient information as requested, ensuring all spelling and details are correct.
-
5.Use checkboxes provided in the form to indicate options for clinical information and other required choices.
-
6.Complete the clinical section with detailed notes about the patient’s condition and anticipated discharge needs.
-
7.Double-check all provided information for accuracy and completeness to avoid potential delays in processing.
-
8.Utilize pdfFiller's tools to highlight any sections of the form that need additional review or signature.
-
9.Once the form is complete, save your changes before finalizing or submitting.
-
10.To submit the form, select the upload button to send it directly via fax or email as appropriate for your referral request.
-
11.Consider downloading a copy of the completed form for your records before submission.
Who is eligible to use the Patient Referral Authorization Form?
Eligibility for the Patient Referral Authorization Form typically includes TRICARE beneficiaries who need referrals for medical services. It's primarily designed for patients receiving care under TRICARE health plans.
What are the submission methods available for this form?
The Patient Referral Authorization Form can be submitted online through pdfFiller or by fax. Ensure you follow the provided submission instructions for efficient processing.
Are there any deadlines associated with submitting this form?
It's important to submit the Patient Referral Authorization Form as soon as medical services are required. Delays in submission could result in disruptions to care or potential denials of authorization.
What supporting documents are required along with this form?
When submitting the Patient Referral Authorization Form, include any necessary supporting documents such as previous medical records, insurance details, and additional provider notes that justify the referral.
What common mistakes should be avoided when completing this form?
Common mistakes include providing incorrect patient information, incomplete sections, and failing to check necessary options. Double-check all entries before submission to avoid delays.
How long does it take to process the referral request after submission?
Processing times for the Patient Referral Authorization Form can vary. Typically, it may take several days, so it's recommended to submit the form well in advance of the required medical services.
What is the purpose of the Patient Referral Authorization Form?
The purpose of the Patient Referral Authorization Form is to obtain authorization for medical services under TRICARE, ensuring that beneficiaries receive care that's medically necessary and covered by their plan.
Related Forms







Related Catalogs
Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.