
Last updated on Aug 20, 2026

Get the free Request for Medical Information
We are not affiliated with any brand or entity on this form
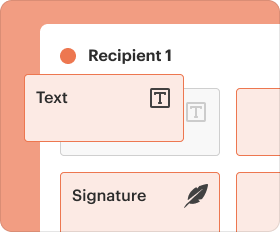
Fill out
Complete the form online in a simple drag-and-drop editor.
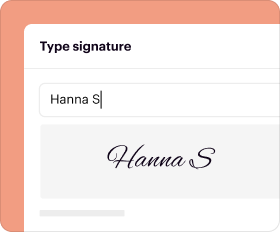
eSign
Add your legally binding signature or send the form for signing.
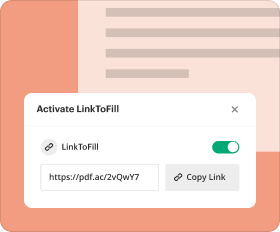
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Request for Medical Information
The Request for Medical Information is a healthcare form used by patients to authorize the disclosure of their protected health information to specified providers.
pdfFiller scores top ratings on review platforms




Who needs Request for Medical Information?
Explore how professionals across industries use pdfFiller.

Request for Medical Information is needed by:
-
Patients requiring access to their medical records
-
Healthcare providers requesting patient information
-
Legal representatives acting on behalf of patients
-
Staff members at Crystal Run Healthcare managing medical requests
-
Insurance companies needing medical documentation
Comprehensive Guide to Request for Medical Information
What is the Request for Medical Information Form?
The Request for Medical Information form is a vital document used by patients receiving care at Crystal Run Healthcare. This form is designed to authorize the disclosure of protected health information to specific healthcare providers, ensuring continuity of care. It is essential to note that this form expires six months after the date it is signed.
By utilizing the medical records release form, patients can effectively manage the sharing of their health information with authorized parties, ensuring that their care processes remain coordinated and comprehensive.
Purpose and Benefits of Using the Request for Medical Information Form
Patients are encouraged to utilize the Request for Medical Information form for several key reasons. First, it ensures that crucial medical details are shared appropriately between providers, facilitating better treatment coordination. Second, authorized disclosure empowers patients to take charge of their health information, reinforcing their rights concerning protected health information.
Advantages of using this form include streamlined communication between various healthcare providers and improved healthcare outcomes through enhanced access to necessary medical records.
Key Features of the Request for Medical Information Form
This form encompasses several critical components that enhance its usability. Key fillable fields include Patient Name, Phone Number, Address, and Date of Birth, all of which are essential for accurate identification and communication. Additionally, the form provides clear instructions that aid in proper completion.
-
Secure features designed to protect sensitive information
-
Comprehensive instructions included for user assistance
-
Specific acknowledgment sections detailing patient rights
Who Should Use the Request for Medical Information Form?
The Request for Medical Information form is specifically aimed at current patients of Crystal Run Healthcare who need to authorize the sharing of their medical information. Scenarios that necessitate the use of this form include referrals to specialists or coordination of care among different providers.
The form benefits patients by ensuring their health information is shared appropriately, while authorized healthcare providers gain access to complete and relevant patient histories, improving treatment quality.
How to Fill Out the Request for Medical Information Form Online
To fill out the Request for Medical Information form online, users should begin by assembling all necessary information prior to accessing the form. This includes personal details such as medical history and the provider's contact information.
-
Access the form on the pdfFiller platform.
-
Enter the required fields accurately, including Patient Name, Phone Number, and Address.
-
Review each section carefully for completeness before submission.
This process ensures a smoother experience and helps to avoid common mistakes.
Submission and Delivery of the Request for Medical Information Form
Once the form is filled out, patients have several options for submission. Utilizing pdfFiller allows for straightforward online submission through the platform, which can streamline the process.
-
Explore various delivery methods, such as direct eDelivery to providers
-
Keep track of associated fees and processing timelines
Familiarizing with submission methods can significantly enhance the efficiency of obtaining medical information.
Common Errors to Avoid When Filling Out the Form
To ensure efficient processing of the Request for Medical Information form, users should be aware of common pitfalls. Key mistakes include inaccurate personal details, omitting required signatures, and failing to provide all necessary information.
-
Double-check all entries before submission to minimize rejections
-
Utilize the review and validation checklist offered within the form
Security and Compliance When Using the Request for Medical Information Form
When handling sensitive information, it is crucial to adhere to strict security protocols. The pdfFiller platform employs state-of-the-art security measures, including 256-bit encryption, to protect user data throughout the process.
Moreover, the platform complies with HIPAA and GDPR standards, ensuring that all protected health information is treated with the utmost confidentiality. This commitment to security provides users with peace of mind when submitting their forms.
What Happens After Submitting the Request for Medical Information Form?
After submitting the Request for Medical Information form, patients can expect a confirmation of receipt from the healthcare provider. Tracking submissions is also an option, allowing users to monitor the processing status.
In case of delays or issues, it is important for users to follow up with the relevant healthcare office to address any potential obstacles.
Easily Manage Your Request for Medical Information with pdfFiller
PdfFiller simplifies the form management process with its user-friendly features. With capabilities like eSigning and instant storage for completed forms, users can manage their documents efficiently.
Additionally, the platform offers quick and easy access to form templates, enhancing the overall experience for users seeking to manage their medical records requests effectively.
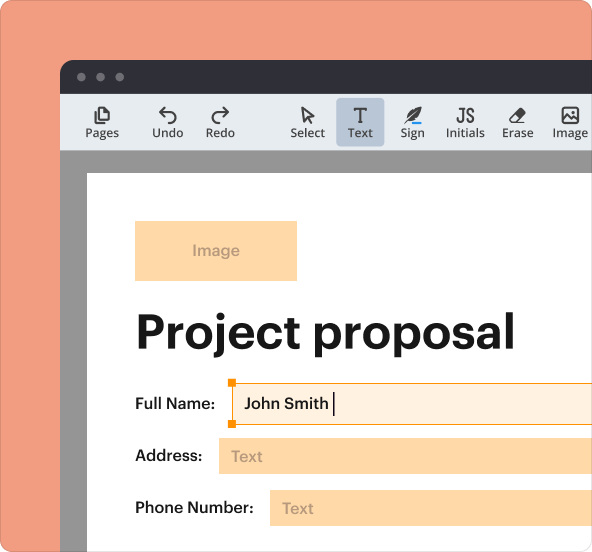
How to fill out the Request for Medical Information
-
1.To access the Request for Medical Information form on pdfFiller, visit the platform's website and use the search bar to locate the form by name.
-
2.Open the form directly in pdfFiller once you find it. Familiarize yourself with the fillable fields and sections provided.
-
3.Prepare by gathering necessary personal information including your name, phone number, address, Social Security number, and date of birth.
-
4.Begin filling in the required fields, starting with your personal details. Use the clear prompts to guide you through each section.
-
5.Carefully input the provider's information who will receive the medical records. Double-check for accuracy to avoid delays.
-
6.Provide a detailed description of the information to be disclosed, ensuring you cover all necessary aspects for the healthcare provider.
-
7.Review the completed form for any errors or missing information. Use the pdfFiller tools to edit as needed.
-
8.Once you’re satisfied with the information, save your progress and prepare to submit the form.
-
9.You can save the filled form as a PDF or directly download it to your device using the options provided on pdfFiller.
-
10.If applicable, choose to submit the form electronically through pdfFiller or print it for mailing. Follow any final submission instructions included.
Who is eligible to fill out the Request for Medical Information form?
The Request for Medical Information form can be filled out by any patient who is seeking to authorize the disclosure of their protected health information, particularly those under the care of Crystal Run Healthcare.
Is there a deadline for submitting the medical information request?
While the form itself does not impose strict deadlines, it is important to submit it promptly to ensure timely access to your medical records, as the authorization expires 6 months from the signing date.
What methods can I use to submit the completed Request for Medical Information form?
You can submit the completed form electronically through pdfFiller or print it out for mailing or hand delivery to the appropriate healthcare provider.
What supporting documents do I need to include with the form?
Generally, you may not need additional supporting documents with the Request for Medical Information form. However, it is important to check with the provider for any specific requirements related to your request.
Are there common mistakes to avoid when filling out the form?
Avoid common mistakes such as leaving fields blank, providing incorrect provider information, or not signing the document. Ensure all details are accurate to prevent delays.
How long does it take to process the Request for Medical Information?
Processing times can vary depending on the provider’s policies and workload. It's advisable to follow up after submitting to check on the status of your request.
What happens if I need to change or revoke my authorization?
If you wish to change or revoke your authorization after signing, you should notify the provider in writing. Details for this should be included in the instructions provided with the form.
Related Forms




Get the latest insights from our blog



If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.