
Last updated on
Oct 2, 2026
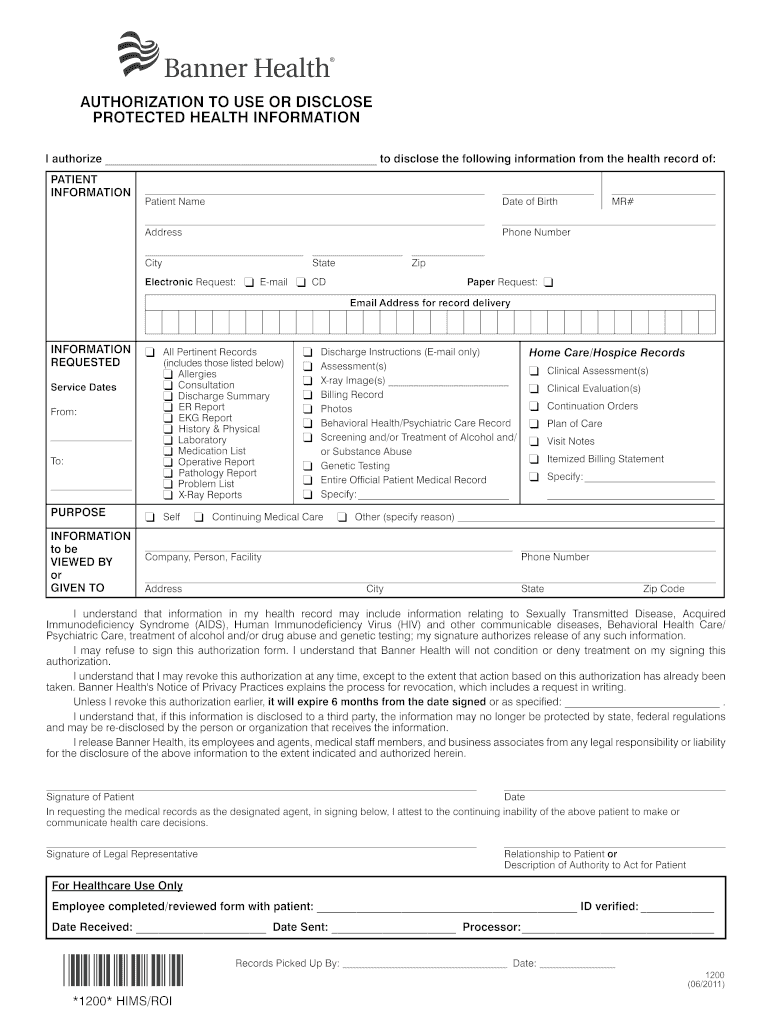
Banner Health Authorization to Use or Disclose Protected Health Information 2011 free printable ...
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Banner Health Authorization to Use or Disclose Protected Health Information
The Authorization to Disclose Protected Health Information is a patient consent form used by patients to authorize the release of their health records.
pdfFiller scores top ratings on review platforms




Who needs Banner Health Authorization to Use or Disclose Protected Health Information?
Explore how professionals across industries use pdfFiller.

Banner Health Authorization to Use or Disclose Protected Health Information is needed by:
-
Patients requiring access to their medical records
-
Legal representatives handling patient health information
-
Healthcare providers requesting patient authorization
-
Insurance companies needing verification of health information
-
Researchers seeking patient consent for studies
-
Hospitals and clinics managing patient records
Comprehensive Guide to Banner Health Authorization to Use or Disclose Protected Health Information
What is the Authorization to Disclose Protected Health Information?
The Authorization to Disclose Protected Health Information is essential in the healthcare sector, enabling patients to grant their healthcare providers permission to release sensitive health records. This authorized release is often known as a health record release form or a patient consent form. This document is crucial for patients and their legal representatives, ensuring the necessary sharing of information while maintaining their rights over personal health data.
Purpose and Benefits of the Authorization to Disclose Protected Health Information
This authorization serves multiple purposes by streamlining communication between healthcare providers and patients. Having timely access to medical records is vital for effective treatment and continuity of care. Additionally, the form protects patient privacy, allowing for the essential exchange of information without compromising confidentiality.
-
Facilitates communication between healthcare professionals and patients.
-
Ensures timely access to medical records for improved treatments.
-
Safeguards patient privacy during necessary information sharing.
Who Needs the Authorization to Disclose Protected Health Information?
The authorization form is necessary for patients wishing to share their health records, as well as for their legal representatives who can sign on their behalf. Various situations, such as transferring care between providers or sharing information with specialists, require this form. However, there may be exceptions where the completion of the form isn’t required, such as in emergencies.
-
Patients and legal representatives must sign the form.
-
The form is needed for care transfers and specialist consultations.
-
Exceptions may occur in specific emergency situations.
How to Fill Out the Authorization to Disclose Protected Health Information: Step-by-Step Guide
Completing the Authorization to Disclose Protected Health Information correctly is crucial for a seamless experience. Start by providing the patient’s name, date of birth, and the type of information requested. Follow up by selecting the purpose of disclosure and the recipient’s details. Ensure that all fields are correctly filled and signed to avoid processing delays.
-
Write the patient’s name and date of birth.
-
Indicate the specific information to be disclosed.
-
Select the purpose of disclosure and the information recipient.
-
Ensure the form is signed accurately by the patient or representative.
Common Errors and How to Avoid Them When Using the Authorization to Disclose Protected Health Information
Filling out the authorization form can lead to several common mistakes that may hinder the disclosure process. Popular errors include missing signatures and incomplete fields. Implementing a thorough review process before submission can prevent these errors and ensure that patient information flows smoothly.
-
Check for missing signatures and incomplete fields.
-
Review the form for accuracy before submission.
-
Double-check recipient details and the information specified for disclosure.
Submitting the Authorization to Disclose Protected Health Information: Methods and Best Practices
When it comes to submitting the completed authorization form, there are various options available. Digital submission, fax, and traditional mail are all viable methods. Including necessary identifiers with the submission can facilitate quicker processing times.
-
Choose between digital, fax, or mail submissions.
-
Include necessary patient identifiers with your submission.
-
Be aware of the estimated timelines for processing submissions.
Security and Compliance of the Authorization to Disclose Protected Health Information
The safety of sensitive health information is paramount in the disclosure process. Organizations must implement stringent security measures to adhere to HIPAA compliance, ensuring that patient data remains protected throughout the authorization process. pdfFiller enhances document security, providing a reliable option for managing sensitive health forms.
-
Implement security measures to protect health information.
-
Ensure HIPAA compliance to maintain data privacy.
-
Utilize tools like pdfFiller for enhanced document security.
Why Choose pdfFiller for Your Authorization to Disclose Protected Health Information
pdfFiller offers a user-friendly platform designed for effortlessly completing forms online. Key features include the ability to eSign documents, store information securely, and share authorization forms with ease. pdfFiller adheres to high compliance and security standards, ensuring that sensitive information is handled responsibly.
-
Utilize pdfFiller for its intuitive interface in completing forms.
-
Take advantage of features like eSigning and secure storage.
-
Trust pdfFiller for its compliance with security standards.
Real-Life Example: Sample Completed Authorization to Disclose Protected Health Information
Visual references can aid in understanding how to fill out the form correctly. An annotated example of a filled-out authorization provides clarity on important components such as formatting and necessary signatures. This model can serve as a guideline for users when completing their forms.
-
Refer to an annotated example for clarification on filling out the form.
-
Focus on key aspects such as proper formatting and signatures.
-
Use the example as a guideline when completing your own authorization form.
How to fill out the Banner Health Authorization to Use or Disclose Protected Health Information
-
1.Access the Authorization to Disclose Protected Health Information form on pdfFiller by typing the form name into the search bar.
-
2.Once you locate the form, click on it to open the fillable PDF.
-
3.Gather necessary information such as patient details, specific health records to disclose, the purpose of disclosure, and the recipient’s information before you begin filling it out.
-
4.Navigate through the form by clicking into each field. Use the text boxes to enter information such as patient name, date of birth, and medical record number.
-
5.Ensure you check the appropriate boxes that apply to your situation, indicating the type of health information to be disclosed.
-
6.Once you have filled in all required fields, review the information for accuracy before finalizing the form.
-
7.Sign the form electronically using pdfFiller’s signature tool. Ensure that the patient and any legal representatives sign where applicable.
-
8.After completing the form, save your changes by clicking on the save button. You can then download the completed form or choose to submit it directly through pdfFiller if needed.
Who is eligible to use the Authorization to Disclose Protected Health Information form?
Any patient wishing to authorize the disclosure of their health records, as well as legal representatives acting on behalf of patients, are eligible to complete this form.
What information do I need to fill out the form?
You will need personal information such as your name, date of birth, MR# (Medical Record Number), the type of information to be disclosed, the purpose of the disclosure, and the recipient's details.
Are there any deadlines for submitting this form?
While there are typically no specific deadlines, it is recommended to submit this authorization as soon as possible, particularly if it is needed for scheduled medical procedures or appointments.
How can I submit the completed form?
After filling out the form on pdfFiller, you can either download a copy to print and mail or submit it electronically through the provided submission methods on pdfFiller.
What common mistakes should I avoid when filling out the form?
Ensure all fields are filled out accurately, especially signature areas. Avoid leaving any critical fields blank, and verify that the intended recipient’s information is correct.
How long does it take to process the authorization once submitted?
Processing times may vary depending on the organization handling the request, but typically you can expect a response within 7 to 14 business days after submission.
Do I need to notarize the form?
No, the Authorization to Disclose Protected Health Information form does not require notarization, although signatures from both the patient and legal representative are necessary.
Banner Health Authorization to Use or Disclose Protected Health Information Form Versions
Related Content
Related Forms




Get the latest insights from our blog



If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.