
Last updated on
Oct 19, 2026

Get the free Prior Authorization Form Dupixent
We are not affiliated with any brand or entity on this form
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Dupixent PA Form
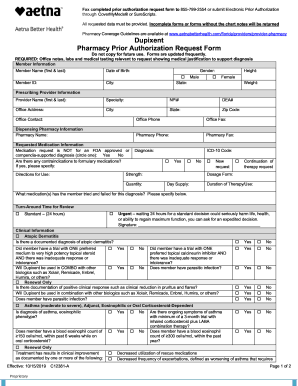
The Prior Authorization Form Dupixent is a medical consent form used by healthcare providers in Virginia to request prior authorization for Dupixent medication.
pdfFiller scores top ratings on review platforms




Who needs Dupixent PA Form?
Explore how professionals across industries use pdfFiller.

Dupixent PA Form is needed by:
-
Healthcare providers who prescribe Dupixent
-
Patients needing Dupixent for medical conditions
-
Medicaid beneficiaries in Virginia
-
Pharmacies filling prescriptions for Dupixent
-
Insurance companies processing prior authorizations
-
Support staff assisting with medical forms
Comprehensive Guide to Dupixent PA Form
What is the Prior Authorization Form Dupixent?
The Prior Authorization (PA) Form Dupixent is a crucial document used by healthcare providers in Virginia to request medication approval for Dupixent. Its primary function is to facilitate access to treatment for patients who require this medication under Medicaid products offered by HealthKeepers, Inc. By completing this form, prescribers can ensure that patients receive the necessary authorization to access the medication they need.
Purpose and Benefits of the Prior Authorization Form Dupixent
The PA Form Dupixent serves several important purposes in the medication approval process. Initially, it clarifies which medical conditions the medication Dupixent is intended to treat, making it easier for prescribers to justify the request. This form benefits both prescribers and patients by streamlining the authorization process and improving access to essential medications for Medicaid patients.
-
Ensures prescribers can effectively request medication approvals.
-
Reduces delays in obtaining necessary medication for patients.
-
Aids in the management of chronic conditions treated by Dupixent.
Key Features of the Prior Authorization Form Dupixent
The Prior Authorization Form Dupixent includes several essential elements that healthcare providers must complete. Required fields include member information, prescriber details, and specific diagnosis information relevant to the treatment. Additionally, the form features checkbox options to indicate various medical conditions, along with a mandatory prescriber’s signature. The form remains valid for one year from the date of signing.
Who Needs the Prior Authorization Form Dupixent?
The audience for the Dupixent PA form includes a variety of healthcare professionals in Virginia, specifically those who are authorized to prescribe medications under Medicaid regulations. This includes physicians, nurse practitioners, and physician assistants who are managing patients eligible for Dupixent. Understanding who qualifies for both prescribing and receiving Dupixent is crucial in ensuring all regulations are met.
-
Prescribers in Virginia who are licensed to request medication approvals.
-
Patients enrolled in Medicaid and diagnosed with conditions treated by Dupixent.
-
Healthcare professionals who assist in filling out or submitting the form.
How to Fill Out the Prior Authorization Form Dupixent Online
Completing the Prior Authorization Form Dupixent online can be achieved through a straightforward process using tools like pdfFiller. The step-by-step instructions for filling out the form include starting with member information, adding correct prescriber details, and selecting the appropriate diagnosis. Each field should be checked for accuracy to minimize errors before submission.
-
Access the Dupixent PA form through pdfFiller.
-
Fill in member and prescriber information accurately.
-
Select appropriate checkboxes for diagnosed conditions.
-
Ensure the prescriber signs the document.
-
Review for completeness before submission.
Submission Methods and Delivery of the Prior Authorization Form Dupixent
When it comes to submitting the Prior Authorization Form Dupixent, several delivery methods are available to ensure that prescribers can choose the most convenient option. Forms can be submitted online, via mail, or by fax, each catering to different preferences and requirements. Be sure to check the estimated processing times to avoid delays in medication access.
-
Online submission for quick and efficient processing.
-
Mailing options for physical copies of the form.
-
Fax submissions for immediate confirmation of delivery.
Common Rejection Reasons and Solutions
Submitting the Prior Authorization Form Dupixent does come with potential pitfalls that prescribers should be aware of. Common rejection reasons include incomplete information, missing signatures, or incorrect diagnosis codes. To avoid these issues, it's important to ensure that all documentation is accurate and thoroughly checked before submission.
-
Verify all mandatory fields are filled out completely.
-
Check that the prescriber’s signature is present and valid.
-
Ensure the diagnosis codes match the medical condition being treated.
Security and Compliance for the Prior Authorization Form Dupixent
The importance of data protection when handling the Prior Authorization Form Dupixent cannot be overstated. pdfFiller ensures secure handling of sensitive patient information by adhering to HIPAA guidelines and implementing 256-bit encryption methods. This commitment to confidentiality safeguards user information during the entire submission process.
Effortless Document Management with pdfFiller
Using pdfFiller offers a host of features that simplify document management for the Prior Authorization Form Dupixent. With capabilities such as eSigning, editing, and converting PDFs, prescribers can efficiently manage their healthcare documentation. Leveraging pdfFiller’s platform enhances accuracy and convenience, ensuring that all forms are completed correctly and submitted securely.
How to fill out the Dupixent PA Form
-
1.Access pdfFiller and search for the 'Prior Authorization Form Dupixent' to open the document.
-
2.Once opened, familiarize yourself with the required fields indicated on the form.
-
3.Gather necessary information such as the patient's medical history, prescriber information, and diagnosis details beforehand for efficient completion.
-
4.Complete each field using pdfFiller's interactive text feature, ensuring all member and prescriber information is accurate and detailed.
-
5.Use the checkboxes to indicate the specific medical conditions for which Dupixent is being prescribed.
-
6.Review all entries carefully for completeness and accuracy before proceeding.
-
7.Add the required prescriber signature by using the signature feature within pdfFiller.
-
8.Once the form is fully completed, double-check all information for any potential errors or omissions.
-
9.Save the form in your pdfFiller account for easy retrieval later, and download a copy for your records if necessary.
-
10.Submit the completed prior authorization form via pdfFiller's submission feature, ensuring it reaches the intended Medicaid provider.
Who is eligible to use the Prior Authorization Form Dupixent?
Healthcare providers who prescribe Dupixent for patients, especially those enrolled in Medicaid in Virginia, are eligible to use this form.
What information is required to complete the form?
You will need detailed patient information, diagnosis details, prescriber information, and a signature from the prescriber to complete the Prior Authorization Form Dupixent.
How should I submit the form after filling it out?
After completing the form on pdfFiller, you can submit it electronically through the platform, or download it and send it to the appropriate Medicaid provider.
Is there a deadline for submitting the authorization request?
While specific deadlines can vary, it is recommended to submit the prior authorization request as soon as possible to avoid delays in treatment.
What common mistakes should I avoid when filling out the form?
Ensure that all fields are filled out accurately, double-check the diagnosis information, and do not forget to include the prescriber's signature to prevent processing delays.
What are the processing times for prior authorization requests?
Processing times can vary; typically, you can expect a response within a few business days after submitting the Prior Authorization Form Dupixent.
Are there any supporting documents required with the form?
Additional supporting documents may be requested based on the medication and diagnosis; typically, previous treatment records may be needed to support the authorization request.
Related Forms






Get the latest insights from our blog



If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.