
Last updated on
Sep 5, 2026

Get the free Patient Registration Form
We are not affiliated with any brand or entity on this form
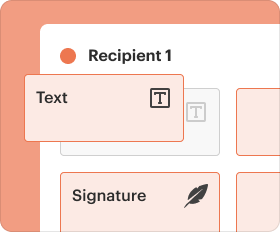
Fill out
Complete the form online in a simple drag-and-drop editor.
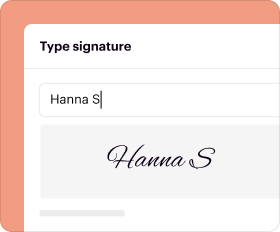
eSign
Add your legally binding signature or send the form for signing.
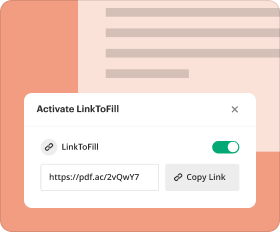
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Patient Registration
The Patient Registration Form is a healthcare document used by providers to collect essential personal and medical information from new patients.
pdfFiller scores top ratings on review platforms




Who needs Patient Registration?
Explore how professionals across industries use pdfFiller.

Patient Registration is needed by:
-
New patients seeking healthcare services.
-
Parents or legally authorized individuals completing forms on behalf of patients.
-
Healthcare providers needing accurate patient data.
-
Administrative staff managing patient registrations.
-
Insurance companies requiring patient information.
-
Medical facilities operating in Indiana.
Comprehensive Guide to Patient Registration
What is the Patient Registration Form?
The Patient Registration Form plays a crucial role in healthcare settings by gathering essential information from new patients. This form typically includes personal details, emergency contacts, insurance information, and medical history. Notably, patient signatures are required, including those from parents or legally authorized individuals, to validate the information provided and authorize medical practices.
Why is the Patient Registration Form Essential in Indiana?
In Indiana, this patient registration form is vital for ensuring compliance with state regulations regarding the collection of patient information. It benefits both healthcare providers and patients by streamlining intake processes and improving record accuracy. Additionally, it is critical to maintain confidentiality and protect patient privacy throughout the registration process.
Key Features of the Patient Registration Form
-
Fillable fields for easy data entry
-
Checkboxes to simplify selection
-
Required signature lines to ensure validation
-
Integration with pdfFiller for editing and sharing
-
Special considerations for medical history and insurance details
Who Needs to Complete the Patient Registration Form?
The primary users of the patient registration form include new patients, parents, or legally authorized individuals. This form is essential during specific situations, particularly a patient's first visit to a healthcare provider. Additionally, some special groups may have unique requirements when filling out the form.
How to Fill Out the Patient Registration Form Online (Step-by-Step)
-
Access the patient registration form on the pdfFiller platform.
-
Edit the fillable fields directly in your browser.
-
Carefully enter information in crucial sections, such as medical history and insurance details.
-
Review all entries to ensure accuracy.
-
Submit the form electronically once completed.
Common Errors to Avoid When Completing the Patient Registration Form
Several common mistakes can arise during the form-filling process. To avoid errors, double-check all entries, particularly personal and insurance information. Additionally, ensure that all required signatures are included to avoid delays in processing.
Securing Your Patient Registration Data
pdfFiller employs robust security measures to protect personal and sensitive information submitted through the patient registration form. It is essential to adhere to HIPAA compliance and data protection standards in healthcare forms. The platform utilizes advanced encryption standards to ensure user privacy and mitigate risks associated with data breaches.
What Happens After You Submit the Patient Registration Form?
Once the patient registration form is submitted, healthcare providers typically follow specific steps for processing the information. Patients can expect communication regarding the next stages, including potential timelines for processing their application. Confirmation notifications may be provided, allowing patients to track their submissions if applicable.
Maximize Your Experience with pdfFiller
Utilizing pdfFiller's comprehensive features can enhance the management of your patient registration form. Users are encouraged to explore other healthcare templates available on the platform. The ease of use promotes efficient filling, signing, saving, and sharing of documents.
How to fill out the Patient Registration
-
1.To access the Patient Registration Form on pdfFiller, visit the pdfFiller website and use the search bar to locate the form by typing 'Patient Registration Form'.
-
2.Once you've found the form, click on it to open it in the pdfFiller interface, where you can view all fillable fields.
-
3.Before filling out the form, gather necessary information such as personal details, emergency contacts, insurance information, and medical history to ensure a smooth process.
-
4.Navigate through the form using the provided fillable fields. Click on each field to enter corresponding information such as your name, address, and phone number.
-
5.If specific fields require a signature, select the signature box and follow the instructions to digitally sign the document.
-
6.After completing the form, take a moment to review all entered information for accuracy, ensuring that there are no missing fields or errors.
-
7.Upon finalizing your review, you can save the form by clicking the 'Save' button, allowing you to easily return to it if needed.
-
8.To download or print the completed form, select the 'Download' option or click on 'Print' to have a hard copy for submission.
-
9.Finally, if required, submit the form directly through pdfFiller by following on-screen instructions to send it electronically to your healthcare provider.
Who is eligible to complete the Patient Registration Form?
The Patient Registration Form can be completed by new patients, or by parents and legally authorized individuals on behalf of patients. Ensure that the signer is authorized to provide medical information.
Is there a deadline to submit the Patient Registration Form?
There is generally no strict deadline, but it is advisable to submit the form before your first appointment to ensure timely processing and avoid delays in care.
What methods can I use to submit the form?
You can submit the completed Patient Registration Form electronically through pdfFiller, or print it out and physically hand it in to the healthcare provider’s office.
What supporting documents do I need?
Typically, you may need to provide documents such as valid identification, insurance cards, and any medical records pertinent to your medical history or previous healthcare.
What common mistakes should I avoid while filling out the form?
Ensure all fields are completed accurately and legibly. Avoid leaving blanks in required fields and double-check the information for typos, especially on contact and insurance details.
How long does it take to process the Patient Registration Form?
Processing time may vary by provider, but typically, your submitted form will be reviewed and processed within a few business days before your appointment.
Can I edit the Patient Registration Form after submitting it?
You can usually edit the form through pdfFiller if you saved a copy before submission. To make changes after submission, contact the healthcare provider's office for assistance.

If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.