
Last updated on
Sep 29, 2026

Get the free Patient Family Partner Direct Deposit Form
We are not affiliated with any brand or entity on this form
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Direct Deposit Form
The Patient Family Partner Direct Deposit Form is a medical billing document used by patients and family partners to set up direct deposit for reimbursement payments.
pdfFiller scores top ratings on review platforms




Who needs Direct Deposit Form?
Explore how professionals across industries use pdfFiller.

Direct Deposit Form is needed by:
-
Patients seeking reimbursement for medical expenses
-
Family partners managing financial matters for patients
-
Healthcare providers needing accurate billing information
-
Accounts Payable Departments in healthcare facilities
-
Insurance companies coordinating direct deposit setups
Comprehensive Guide to Direct Deposit Form
What is the Patient Family Partner Direct Deposit Form?
The Patient Family Partner Direct Deposit Form is a crucial document designed to facilitate the setup of direct deposit for reimbursement payments. This form is primarily utilized by patients and their family partners to ensure that they receive funds swiftly and securely. Users are required to provide essential personal and banking information, including details such as a void cheque or a Banking Information Verification Form to confirm their account details.
Purpose and Benefits of the Patient Family Partner Direct Deposit Form
This form offers several notable advantages, enhancing user experience and the reimbursement process. Key benefits include:
-
Convenience of receiving payments directly into a bank account.
-
Faster reimbursement processes compared to traditional methods.
-
High level of accuracy in financial transactions, reducing the incidence of errors.
-
Secure handling of sensitive information, ensuring privacy and protection.
Who Needs the Patient Family Partner Direct Deposit Form?
Individuals who will benefit from the Patient Family Partner Direct Deposit Form include patients and their family partners. This form becomes essential in various situations, such as when:
-
A patient is seeking reimbursement for medical expenses.
-
A family partner is managing financial matters related to a patient’s care.
-
Specific eligibility criteria exist, such as needing to provide proof of banking information.
How to Fill Out the Patient Family Partner Direct Deposit Form Online (Step-by-Step)
Filling out the Patient Family Partner Direct Deposit Form is straightforward with these steps:
-
Download the form from the official site.
-
Fill in required fields, including your NAME, ADDRESS, and EMAIL.
-
Provide your PHONE and CELL numbers as needed.
-
Affix your signature and date in the designated areas.
-
Double-check your entries for correctness before submission.
Common Errors and How to Avoid Them
To ensure successful completion of the form, be mindful of the following common errors:
-
Leaving important fields incomplete.
-
Providing an incorrect email address, hampering communication.
-
Failing to review the form thoroughly before submission.
Double-check all entries and validate your information to minimize mistakes.
Submission Methods and What Happens After You Submit the Form
To submit your completed Patient Family Partner Direct Deposit Form, follow these instructions:
-
Email or deliver the form to the Accounts Payable Department at KCMH.
-
Expect a confirmation or tracking update regarding your submission.
-
Understand the processing time and the subsequent steps involved.
Security and Compliance Considerations for the Patient Family Partner Direct Deposit Form
Ensuring the security of sensitive information is paramount. This form utilizes 256-bit encryption to protect data and complies with relevant regulations such as HIPAA and GDPR. Users can be assured of safe handling practices of their financial data during the submission process.
How pdfFiller Can Help with the Patient Family Partner Direct Deposit Form
pdfFiller enhances the user experience with the Patient Family Partner Direct Deposit Form through its array of features. Users can benefit from:
-
Easy text and image editing capabilities.
-
Convenient eSigning options, eliminating the need for printed documents.
-
Online tools that simplify form filling without downloads.
Utilizing pdfFiller promotes creation of a completed and secure form, improving efficiency.
Sample or Example of a Completed Patient Family Partner Direct Deposit Form
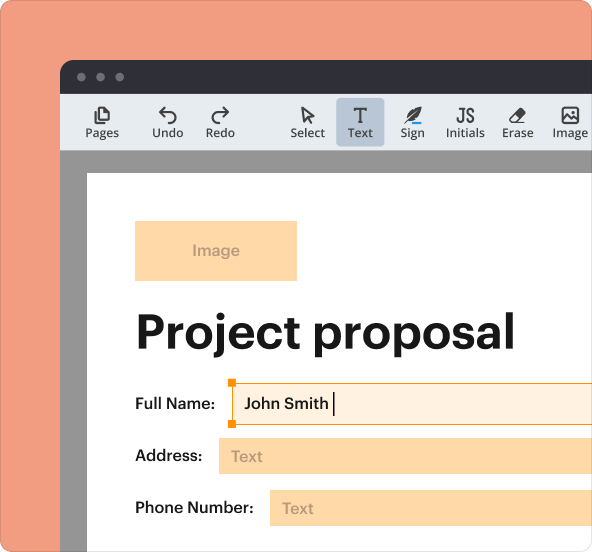
A filled version of the Patient Family Partner Direct Deposit Form serves as a useful reference. The visual guide shows completed fields, clarifying how to accurately fill out each section. Users can also access this form to download and complete their own version.
Final Steps for Successful Submission
To wrap up the form process effectively, consider these critical steps:
-
Ensure all fields are complete and accurate before final submission.
-
Utilize pdfFiller to streamline the form-filling process.
-
Remember to check the application status post-submission for updates.
How to fill out the Direct Deposit Form
-
1.Access the Patient Family Partner Direct Deposit Form on pdfFiller by searching for its name in the search bar.
-
2.Once the form is open, review the fields that need to be filled out. The fillable sections include NAME, ADDRESS, EMAIL, PHONE NUMBER, and CELL NUMBER.
-
3.Before completing the form, gather all necessary personal information and banking details, including a void cheque or Banking Information Verification Form to ensure accuracy.
-
4.Begin filling out each field carefully, entering the required information. Use pdfFiller’s tools to check for any spelling errors or missing data.
-
5.As you fill in the form, look for the checkboxes concerning email notifications regarding deposit details, and select your preference.
-
6.After completing all required fields, double-check all entries for completeness and accuracy. Ensure that your signature and date are included at the bottom of the form.
-
7.Once you confirm that all information is correct, review the completed form using the preview function on pdfFiller.
-
8.To save your form, click on the save option or download it directly for personal records. You can also submit it through the designated submission option provided on pdfFiller.
Who is eligible to fill out the Patient Family Partner Direct Deposit Form?
The form is intended for patients and their family partners who require a direct deposit setup for reimbursement payments from healthcare providers.
What supporting documents are needed when submitting the form?
You must provide personal and banking information, including a void cheque or Banking Information Verification Form, alongside your completed Patient Family Partner Direct Deposit Form.
How can I submit the completed form?
After completing the form, you can submit it electronically via pdfFiller or print and send it directly to the Accounts Payable Department at KCMH in Prince Edward Island.
What are common mistakes to avoid when filling out this form?
Ensure all fields are filled out completely and accurately. Common mistakes include misspelling names, providing incorrect banking details, and forgetting to sign the form.
Is there a deadline for submitting this form?
While specific deadlines may not be indicated, it is advisable to submit the form as soon as possible to ensure timely processing of your reimbursement.
How long does it take to process the direct deposit once the form is submitted?
Processing times can vary, but typically it takes a few business days after submission. Check with your healthcare provider for specific timelines.
Can I make changes to the form after submitting it?
If changes are necessary after submission, contact the Accounts Payable Department promptly to discuss how to proceed with corrections or updates.
Related Forms





Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.