
Last updated on
Oct 8, 2026

Get the free Authorization for Use of Protected Health Information
We are not affiliated with any brand or entity on this form
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Health Info Authorization
The Authorization for Use of Protected Health Information is a healthcare form used by patients or their representatives to authorize the release of medical records.
pdfFiller scores top ratings on review platforms




Who needs Health Info Authorization?
Explore how professionals across industries use pdfFiller.

Health Info Authorization is needed by:
-
Patients seeking to access their medical records.
-
Representatives authorized to manage a patient's health information.
-
Healthcare providers requiring approval to share medical information.
-
Insurance companies requesting verification of medical records.
-
Legal representatives handling health-related cases.
Comprehensive Guide to Health Info Authorization
What is the Authorization for Use of Protected Health Information?
The Authorization for Use of Protected Health Information is a critical form in the healthcare context, enabling patients and their representatives to authorize the release of medical records. This form serves to clarify the patient's intentions regarding the management of their medical information, ensuring that only designated individuals can access sensitive details. By using the health information authorization form, patients gain control over who views their protected health information, fostering better communication with healthcare providers.
Purpose and Benefits of the Authorization for Use of Protected Health Information
The authorization for use of protected health information is essential for patients and their representatives to facilitate the release of health information. Through this process, individuals can exercise control over their personal health data, which enhances interaction with medical professionals. Key benefits include improved coordination of care, a streamlined approach to referrals, and the ability to manage medical records efficiently.
-
Empowers patients to control their health information
-
Enhances communication with healthcare providers
-
Facilitates timely access to necessary medical records
Key Features of the Authorization for Use of Protected Health Information
Essential components of the authorization form include required signatures, details of information to be disclosed, and patient rights. The form must include the patient’s or representative’s signature, specifying the breadth of disclosure required, such as dates and types of information. An understanding of privacy policies is crucial, ensuring patients know their rights to revoke the authorization at any time.
-
Patient and representative signatures are mandatory
-
Clear identification of information to be disclosed
-
Information on patient rights concerning privacy
Who Needs the Authorization for Use of Protected Health Information?
This form is required for various individuals who may need to obtain medical records. Typically, this includes patients and their legal representatives. Scenarios necessitating the release of medical records include referrals to specialists and processing insurance claims, highlighting the form's role in healthcare operations.
Eligibility Criteria for the Authorization for Use of Protected Health Information
Patients or their legal representatives are eligible to authorize the release of protected health information. Generally, the form can be signed by individuals who have reached the age of majority, although some circumstances may allow minors to authorize under specific regulations. Understanding these eligibility criteria ensures proper compliance during the authorization process.
How to Fill Out the Authorization for Use of Protected Health Information Online (Step-by-Step)
To complete the authorization form online, follow these steps:
-
Access the form on pdfFiller.
-
Fill in the required fields with accurate personal information.
-
Select the type of health information to be disclosed.
-
Provide the purpose for the authorization.
-
Review all entries for accuracy before submitting.
Each field will have guidance, ensuring users understand what specific information to disclose.
Common Errors and How to Avoid Them When Submitting the Authorization for Use of Protected Health Information
When filling out the authorization form, several common mistakes can arise. Missing signatures and providing incorrect information can delay processing and result in denials. Users are encouraged to double-check all entries to ensure completeness and accuracy before final submission.
-
Ensure all signatures are present
-
Verify the accuracy of personal information
-
Check that disclosure details are clearly specified
Security and Compliance for the Authorization for Use of Protected Health Information
pdfFiller employs robust security measures to ensure data security and compliance with HIPAA and GDPR. It is essential to handle sensitive health information with the utmost care, safeguarding against unauthorized access. Utilizing a secure platform like pdfFiller assures users that their submissions are protected throughout the process.
Submission Methods and What Happens After You Submit
There are various submission methods available for the authorization form, including online and mail options. After submission, individuals can expect a confirmation notifying them of receipt, along with an outline of the potential timelines for processing their requests. This structured approach helps patients remain informed throughout the process.
Get Started with pdfFiller for Your Authorization for Use of Protected Health Information
pdfFiller is the ideal platform for managing your authorization for use of protected health information. The platform offers a user-friendly experience, allowing for easy filling and submission of your health information authorization forms. With top-tier security and convenience features, pdfFiller simplifies the process of managing sensitive medical records.
How to fill out the Health Info Authorization
-
1.To begin, access pdfFiller and locate the 'Authorization for Use of Protected Health Information' form from the list of available healthcare forms. Click on the form to open it.
-
2.Once the form is open, familiarize yourself with the layout. Use the toolbar to navigate between the different sections of the form, ensuring you can see all fields that require completion.
-
3.Before filling out the form, gather necessary information such as patient identification details, the specific medical records you need, and the purpose for which the records are being requested.
-
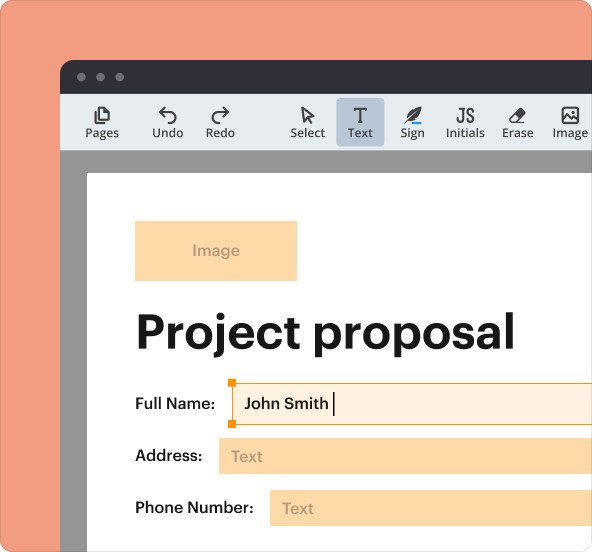
4.Start filling in the required fields by clicking on each blank space. Use pdfFiller’s typing tool to enter information directly into the form.
-
5.If applicable, check the boxes next to relevant options regarding the types of information to be disclosed. This helps specify the medical records that need to be released.
-
6.After completing the form, review all entries carefully to ensure accuracy. Make sure all required signatures are included and that the dates are correct.
-
7.To finalize the process, save your progress periodically. Once completed, you can download the form directly from pdfFiller or submit it using the provided submission options.
-
8.Consider printing the document for your records before submission. If needed, utilize the 'Share' feature within pdfFiller to send the completed form directly to the intended recipient.
Who is eligible to use the Authorization for Use of Protected Health Information?
Patients or their authorized representatives can use this form to grant permission for the release of their medical records. Proper authorization ensures compliance with health information privacy regulations.
Is there a deadline for submitting this authorization form?
There may not be a strict deadline for submitting this form; however, prompt submission is advisable to avoid delays in accessing necessary medical records.
How do I submit the completed form?
Once the form is completed on pdfFiller, you have options to download it for mailing, print it for hand delivery, or submit it electronically through the healthcare provider’s portal, if available.
What supporting documents do I need to submit with this form?
Typically, no additional documents are required aside from the completed form itself. However, verification of identity may be necessary, especially if a representative is acting on behalf of the patient.
What are common mistakes to avoid when filling out this form?
Ensure all required fields are completed, double-check spelling of names and dates, and confirm that all necessary signatures are provided to prevent processing delays.
How long does it take to process this authorization once submitted?
Processing times can vary based on the healthcare provider’s policies, but typically, you should expect a response within a week after submission.
Can I revoke this authorization after signing it?
Yes, patients have the right to revoke their authorization at any time by submitting a written request to the healthcare provider, but this action will not affect any disclosures made prior to the revocation.
Related Forms






Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.