
Last updated on
Oct 20, 2026

Get the free Indiana Health Coverage Programs Prior Authorization Request Form
We are not affiliated with any brand or entity on this form
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Indiana Prior Authorization Form
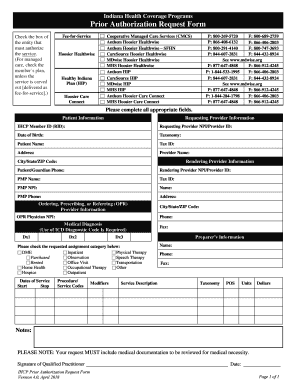
The Indiana Health Coverage Programs Prior Authorization Request Form is a medical document used by healthcare providers in Indiana to request prior authorization for medical services.
pdfFiller scores top ratings on review platforms




Who needs Indiana Prior Authorization Form?
Explore how professionals across industries use pdfFiller.

Indiana Prior Authorization Form is needed by:
-
Healthcare providers in Indiana
-
Physicians requesting prior authorization
-
Healthcare administrators managing patient services
-
Insurance professionals processing claims
-
Medical billing specialists
-
Patients seeking coverage approval
Comprehensive Guide to Indiana Prior Authorization Form
What is the Indiana Health Coverage Programs Prior Authorization Request Form?
The Indiana Health Coverage Programs Prior Authorization Request Form is a crucial document for healthcare providers in Indiana, facilitating the process of prior authorization for various medical services. Prior authorization serves as a mechanism for ensuring that patients receive medically necessary services while allowing insurance payers to manage costs effectively. This form plays an essential role in maintaining coordinated care between healthcare providers and patients, ultimately affecting treatment access and financial implications.
Purpose and Benefits of the Indiana Health Coverage Programs Prior Authorization Request Form
The primary purpose of the Indiana Health Coverage Programs Prior Authorization Request Form is to enhance communication and coordination in healthcare delivery. Utilizing this prior authorization request can lead to improved care coordination, ultimately benefiting both practitioners and patients. Key advantages include:
-
Timely approvals for necessary treatments.
-
Better tracking of denied treatment requests.
-
Reduction in healthcare costs through efficient resource management.
Who Needs the Indiana Health Coverage Programs Prior Authorization Request Form?
This form is primarily required to be completed by qualified practitioners who provide services that necessitate prior authorization. Situations triggering the need for this form typically involve specific medical treatments or procedures that require approval before the service is rendered. Stakeholders including patients seeking care and healthcare practitioners filing the forms must understand these requirements to ensure compliance.
How to Fill Out the Indiana Health Coverage Programs Prior Authorization Request Form Online (Step-by-Step)
Completing the Indiana Health Coverage Programs Prior Authorization Request Form online via pdfFiller is straightforward. Follow these steps to ensure accurate submission:
-
Access the form through pdfFiller.
-
Enter the 'IHCP Member ID' and 'Patient Name' in the designated fields.
-
Complete all required fields, taking care to provide complete and accurate information.
-
Review the form carefully for any errors.
-
Sign the form as a qualified practitioner.
-
Submit the form following the provided instructions.
Common Errors and How to Avoid Them When Completing the Indiana Health Coverage Programs Prior Authorization Request Form
Filling out the Indiana Health Coverage Programs Prior Authorization Request Form can present pitfalls. Common errors include:
-
Incomplete patient or provider information.
-
Missing signatures or required fields.
-
Incorrect medical diagnosis codes.
To avoid these mistakes, practitioners should implement strategies such as double-checking all entries and ensuring all required documentation is attached before submission.
How to Submit the Indiana Health Coverage Programs Prior Authorization Request Form
The submission process for the Indiana Health Coverage Programs Prior Authorization Request Form allows for several methods. Practitioners can submit the form via:
-
Online through the pdfFiller platform.
-
Mail, using the address provided for submission.
-
Fax, where applicable.
Ensure that any additional documentation required for the submission is included, and confirm receipt with the Indiana health authorities if necessary.
What Happens After You Submit the Indiana Health Coverage Programs Prior Authorization Request Form?
Upon submission, the Indiana health authorities review the request for prior authorization. The time frames for approval or denial notifications can vary, so it is important to remain attentive to communication from the authorities. Should approval be denied, practitioners must be prepared to understand the rationale and navigate the appeals process.
Security and Privacy Considerations for the Indiana Health Coverage Programs Prior Authorization Request Form
Security is paramount when dealing with sensitive patient information. pdfFiller employs robust measures to ensure data security, including:
-
256-bit encryption for data protection.
-
Compliance with HIPAA and GDPR regulations.
Practitioners must also be aware of record retention requirements and privacy laws to maintain compliance when handling such forms.
Enhanced Features of pdfFiller When Using the Indiana Health Coverage Programs Prior Authorization Request Form
pdfFiller offers a variety of features to enhance the experience of using the Indiana Health Coverage Programs Prior Authorization Request Form, including:
-
eSigning capabilities for quick form approval.
-
Form editing functionalities to ensure accuracy.
-
Tracking tools for monitoring submission progress.
These features streamline the prior authorization process, making it more efficient for both practitioners and healthcare providers.
Ready to Simplify Your Prior Authorization Process?
By utilizing pdfFiller, practitioners can streamline the process of filling out the Indiana Health Coverage Programs Prior Authorization Request Form. The platform provides a user-friendly experience and ensures the security of personal data while managing healthcare documentation effectively.
How to fill out the Indiana Prior Authorization Form
-
1.Access the Indiana Health Coverage Programs Prior Authorization Request Form on pdfFiller by searching for the form in the provided templates.
-
2.Once you locate the form, click on it to open the fillable document in the pdfFiller interface.
-
3.Familiarize yourself with the layout of the form and the various fields that need to be completed.
-
4.Before you begin filling out the form, gather essential information such as the IHCP Member ID, patient details, and specific medical diagnosis codes.
-
5.Fill in the patient information section, ensuring that you accurately enter the patient name and required details.
-
6.Next, proceed to the service details section, providing comprehensive information on the medical services being requested.
-
7.Utilize the checkboxes and other fillable options to ensure all required areas are properly completed.
-
8.Do not forget to fill in the signature field for the Qualified Practitioner, as this is a mandatory requirement for submission.
-
9.After filling in all fields, take a moment to review the entire form for accuracy and completeness.
-
10.Once satisfied, save your work by using the save function in pdfFiller. You can also download the form or submit it directly through the platform by following the on-screen instructions.
Who is eligible to submit the Indiana Health Coverage Programs Prior Authorization Request Form?
The form is designed for healthcare providers in Indiana who need to request prior authorization for medical services on behalf of their patients.
What information is required to complete the form?
You will need the IHCP Member ID, patient name, medical diagnosis codes, and specifics about the requested services to complete the form accurately.
How do I submit the completed form?
You can submit the completed form directly through pdfFiller or download it and submit it via email or postal mail, depending on the specific submission instructions provided.
Are there deadlines I need to be aware of when submitting this form?
While specific deadlines may vary based on insurance provider policies, it is generally recommended to submit prior authorization requests as early as possible to avoid delays in patient care.
What mistakes should I avoid when filling out the form?
Common mistakes include incomplete fields, incorrect patient information, and failure to provide the required signature from a qualified practitioner.
How long does it typically take to process the form?
Processing times can vary depending on the insurer, but it's advisable to allow several business days for authorization decisions to be made.
Do I need to include supporting documents with my submission?
Typically, you may need to include medical records or additional documentation that supports the request, so it's wise to check with the specific insurance guidelines.
Related Forms







Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.