
Last updated on
Oct 2, 2026
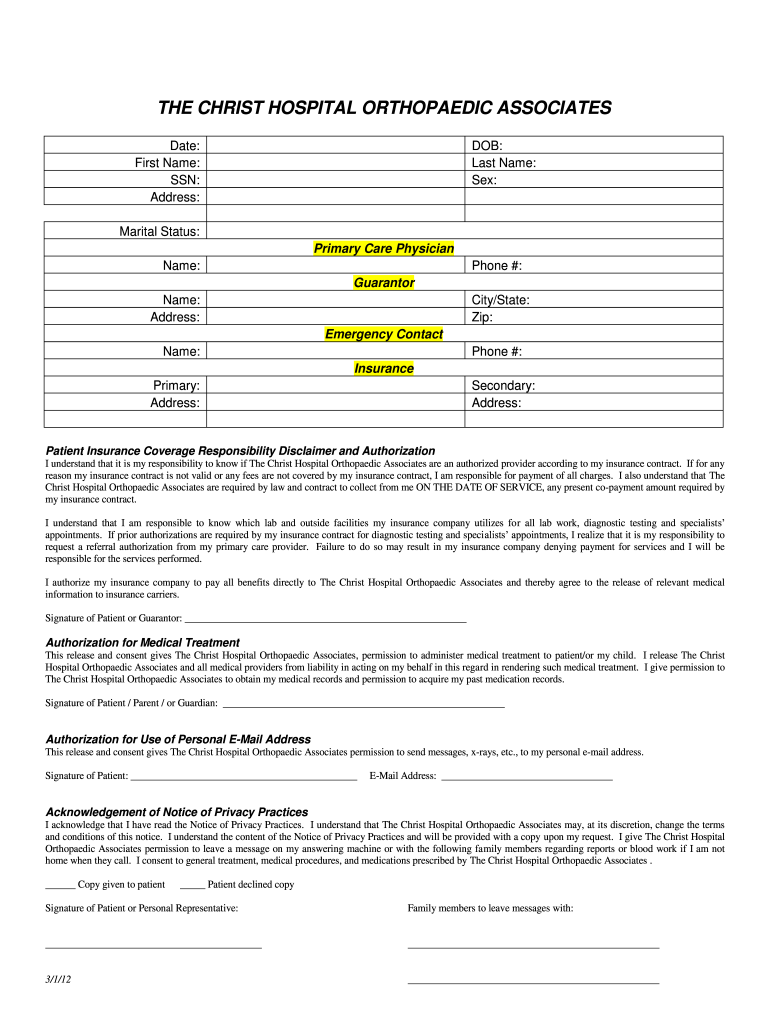
OH Christ Hospital Orthopaedic Associates HIPAA Form 2012-2026 free printable template
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is OH Christ Hospital Orthopaedic Associates HIPAA Form
The Patient Insurance Coverage Disclaimer and Authorization is a type of document used by patients to acknowledge their financial responsibilities for insurance coverage and authorize medical treatment.
pdfFiller scores top ratings on review platforms




Who needs OH Christ Hospital Orthopaedic Associates HIPAA Form?
Explore how professionals across industries use pdfFiller.

OH Christ Hospital Orthopaedic Associates HIPAA Form is needed by:
-
Patients seeking medical treatment
-
Parents or guardians of minor patients
-
Personal representatives of patients
-
Healthcare providers requiring authorization
-
Insurance companies needing documentation
-
Medical facilities for compliance
-
Legal guardians or conservators
Comprehensive Guide to OH Christ Hospital Orthopaedic Associates HIPAA Form
What is the Patient Insurance Coverage Disclaimer and Authorization?
The Patient Insurance Coverage Disclaimer and Authorization form is a crucial document used by The Christ Hospital Orthopaedic Associates to inform patients of their insurance responsibilities. This form functions as a key element in the healthcare process by ensuring that patients understand their obligations regarding medical treatment authorization.
Patients engage with the form to clarify their insurance responsibilities and authorize the provision of necessary medical treatments. It is essential for individuals to comprehend the implications of medical treatment authorization, as well as the privacy practices in place to protect their health information.
Purpose and Benefits of the Patient Insurance Coverage Disclaimer and Authorization
This form is designed to clarify the financial responsibilities that patients and their guardians must acknowledge. By providing clarity on billing and insurance coverage, the form enhances transparency between patients and healthcare providers, leading to an improved healthcare experience.
Proper authorization for medical treatment also streamlines care delivery, enabling timely access to necessary health services. The form reinforces patient privacy practices, thereby fostering a sense of trust between patients and The Christ Hospital Orthopaedic Associates.
Who Needs the Patient Insurance Coverage Disclaimer and Authorization?
The Patient Insurance Coverage Disclaimer and Authorization must be signed by several parties, each playing distinct roles in the process. The primary signatories include:
-
Patient
-
Guarantor
-
Parent or Guardian
-
Personal Representative
Understanding when and why each individual needs to sign the form is critical. Multiple signatures are often necessary to ensure comprehensive authorization and consent for medical treatment, aligning all parties on their responsibilities.
How to Fill Out the Patient Insurance Coverage Disclaimer and Authorization Online (Step-by-Step)
Filling out the Patient Insurance Coverage Disclaimer and Authorization online requires adherence to specific steps. Here’s a straightforward guide to completing the form:
-
Enter your Date of Birth (DOB) and Date.
-
Provide your First Name and Last Name as requested.
-
Fill in the signature fields accurately as per your role (Patient, Guarantor, etc.).
-
Ensure all required fields are completed to avoid processing delays.
Taking care to fill out personal information with precision is crucial for the successful completion of this form.
Field-by-Field Instructions for the Patient Insurance Coverage Disclaimer and Authorization
Each field in the Patient Insurance Coverage Disclaimer and Authorization serves a specific purpose. Here is a breakdown of significant entries:
-
First Name: Required for identification.
-
Last Name: Necessary for formal records.
-
Date: Indicates when the form was filled out.
-
Signature fields: Must be completed by all signatories to validate the form.
Be aware of common mistakes, such as omitting required fields or illegible handwriting, which can delay processing. Following best practices ensures the form is completed accurately.
How to Sign the Patient Insurance Coverage Disclaimer and Authorization
Signing the Patient Insurance Coverage Disclaimer and Authorization involves understanding the requirements based on your designated role. It’s essential to know that:
-
Guarantors and patients have distinct signature requirements.
-
Digital signatures are legally recognized, providing convenience.
-
Tools like pdfFiller facilitate the eSigning process, ensuring secure and efficient submissions.
Understanding these aspects of signing helps streamline the completion of the form.
Where to Submit the Patient Insurance Coverage Disclaimer and Authorization
Proper submission methods for the Patient Insurance Coverage Disclaimer and Authorization are vital. Patients can submit their forms through the following methods:
-
Online submission via secure platforms.
-
Mailing the completed form to the appropriate office.
-
In-person delivery at The Christ Hospital Orthopaedic Associates.
Each submission method may have associated processing times and potential fees, so it’s advisable to check before submitting.
Security and Compliance for the Patient Insurance Coverage Disclaimer and Authorization
Ensuring the security of sensitive patient information is paramount. The Patient Insurance Coverage Disclaimer and Authorization aligns with compliance standards through the use of platforms like pdfFiller, which adheres to:
-
HIPAA regulations to protect personal health information.
-
GDPR principles for data security and privacy.
-
256-bit encryption methods for data protection.
These measures are crucial in maintaining the confidentiality and integrity of patient records.
Examples and Templates of the Patient Insurance Coverage Disclaimer and Authorization
To assist users in the completion of the Patient Insurance Coverage Disclaimer and Authorization, examples and templates are available. Such resources include:
-
A sample filled-out form that demonstrates appropriate completion.
-
Guidelines on avoiding common pitfalls during the completion process.
-
Access to pdfFiller resources that offer additional support.
Utilizing these templates can significantly enhance the form-filling experience.
Explore More with pdfFiller to Complete Your Patient Insurance Coverage Disclaimer and Authorization
To enhance your form-filling experience, pdfFiller provides various capabilities for users. It offers:
-
eSigning features for quick and secure authorization.
-
Edit and fill options that simplify form completion.
-
Accessible online tools for efficient document management.
Leveraging pdfFiller for your Patient Insurance Coverage Disclaimer and Authorization ensures a seamless process from start to finish.
How to fill out the OH Christ Hospital Orthopaedic Associates HIPAA Form
-
1.Access the Patient Insurance Coverage Disclaimer and Authorization form by visiting pdfFiller’s website and searching for the form title.
-
2.Open the form in the pdfFiller interface where you can see a fillable PDF layout.
-
3.Before filling out the form, gather necessary information such as your personal details, insurance policy information, and any required signatures.
-
4.Begin by entering your date of birth and names in the designated fields, ensuring all spelling is correct.
-
5.Use checkboxes to indicate your acknowledgment of the financial responsibilities and permissions granted on the form.
-
6.Carefully review the sections regarding insurance obligations and medical treatment authorization to ensure comprehension.
-
7.In the signature fields, provide your signature and the date. If filling in on behalf of a child or another individual, include your relation to the patient.
-
8.After completing all sections, review the form for completeness and accuracy at the top right of the form.
-
9.Once satisfied, save your completed form by clicking ‘Save’ in the top menu or download it directly to your device.
-
10.To submit, look for an option to send the form electronically or print it for manual submission based on the requirements specified.
Who is required to sign the Patient Insurance Coverage Disclaimer?
The Patient Insurance Coverage Disclaimer requires signatures from the patient, parent, guardian, or personal representative. Each role must provide appropriate authorization to confirm understanding of the insurance obligations.
Is there a deadline for submitting this form?
While there isn't a specific deadline mentioned for submitting this form, it is important to complete and submit it before any medical treatment is provided to avoid potential financial disputes.
What should I do if I make a mistake while filling out the form?
If you make a mistake, utilize the pdfFiller's editing features to correct the errors before saving or submitting your form. Check all fields carefully for accuracy to prevent issues later.
Can I submit the form online?
Yes, you can submit the Patient Insurance Coverage Disclaimer form online through pdfFiller's submission options, or you may choose to print and hand-deliver it if preferred.
What information do I need to gather before filling out the form?
Prepare to input your personal information, insurance details, and any necessary signatures from authorized signatories. Having these ready will expedite the form completion process.
Are there any fees associated with submitting this form?
Generally, there are no direct fees associated with submitting the Patient Insurance Coverage Disclaimer. However, confirm with the healthcare provider if any fees apply to processing your medical treatment.
How long does it take to process this form?
Processing times can vary based on the healthcare provider's procedures. It is advisable to submit the form as early as possible to ensure compliance and timely authorization for your medical care.
Related Content
Related Forms







Related Catalogs

If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.