
Last updated on
Oct 31, 2026
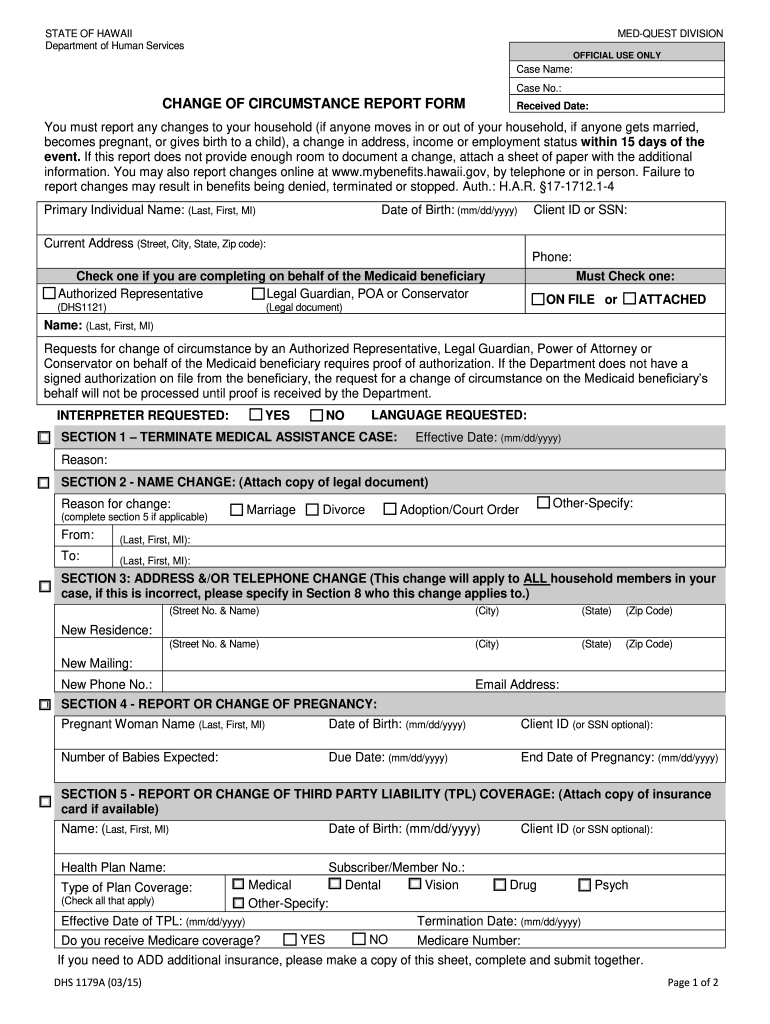
HI DHS 1179A 2015-2026 free printable template
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is HI DHS 1179A
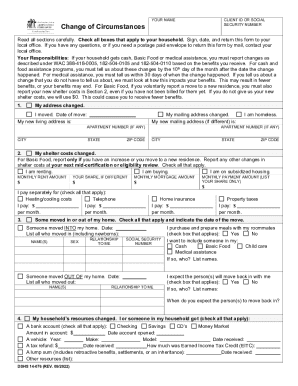
The Hawaii Medicaid Change of Circumstance Report Form is a government document used by Medicaid beneficiaries in Hawaii to report any changes in their circumstances, such as household composition and income.
pdfFiller scores top ratings on review platforms




Who needs HI DHS 1179A?
Explore how professionals across industries use pdfFiller.

HI DHS 1179A is needed by:
-
Medicaid beneficiaries living in Hawaii
-
Authorized representatives for Medicaid beneficiaries
-
Legal guardians, POAs, or conservators of Medicaid beneficiaries
-
Individuals reporting income changes to Medicaid
-
Those updating address information with Medicaid
Comprehensive Guide to HI DHS 1179A
What is the Hawaii Medicaid Change of Circumstance Report Form?
The Hawaii Medicaid Change of Circumstance Report Form is designed for Medicaid beneficiaries to report important changes pertaining to their circumstances. It serves to maintain the accuracy of information related to household and income, ensuring beneficiaries receive appropriate support. Individuals are required to report specific changes, including alterations in household members, address updates, and variations in income, to comply with Medicaid regulations.
Who Needs to Complete the Hawaii Medicaid Change of Circumstance Report Form?
This form must be completed by several key audiences, including the primary individuals, their authorized representatives, and legal guardians. Eligibility criteria for using this form includes individuals receiving Medicaid benefits who experience changes in their family or financial status. Common scenarios that necessitate the form include a change in income or relocating to a new address.
When and Why Should You File the Hawaii Medicaid Change of Circumstance Form?
It is imperative to file the Hawaii Medicaid Change of Circumstance Report Form within 15 days of experiencing a relevant event. Failure to do so may lead to severe consequences, such as denial or termination of benefits, affecting one’s access to necessary healthcare. Maintaining accurate information is crucial for sustaining Medicaid eligibility and ensuring continued support.
How to Fill Out the Hawaii Medicaid Change of Circumstance Report Form Online
Filling out the form digitally through pdfFiller is straightforward. Follow these steps:
-
Access pdfFiller’s platform.
-
Locate the Hawaii Medicaid Change of Circumstance Report Form.
-
Gather necessary information such as your Client ID and other personal data.
-
Complete the form by entering required details in the provided fields.
-
Review your entries for accuracy before submission.
Using an online platform offers significant convenience over traditional paper forms, allowing for easier edits and submissions.
Field-by-Field Instructions for the Hawaii Medicaid Change of Circumstance Form
Understanding each section of the form is essential for accurate completion. Key fields include:
-
Primary Individual Name (Last, First, MI)
-
Date of Birth (mm/dd/yyyy)
-
Client ID or SSN
-
Current Address and Phone Number
Additionally, the form includes sections to report changes in household composition, income levels, and pregnancy. Ensure all information provided is accurate and detailed to facilitate proper processing.
Submission Methods for the Hawaii Medicaid Change of Circumstance Report Form
Users can conveniently submit the form online through pdfFiller. Alternatives include printing and mailing the completed form to the appropriate Medicaid office. Be aware of any associated fees for submission and check processing times to stay informed about the status of your application.
Common Errors to Avoid When Completing the Hawaii Medicaid Change of Circumstance Form
When filling out the form, individuals should watch for frequent mistakes and how to avoid them. Common errors include:
-
Inaccurate personal information.
-
Failure to include all required signatures.
-
Omitting necessary supporting documents.
Utilizing a review and validation checklist can be beneficial to ensure all entries are correct before submission.
How pdfFiller Can Help with the Hawaii Medicaid Change of Circumstance Report Form
pdfFiller simplifies the form-filling process with features that enhance user experience, including:
-
Fillable forms for easy completion.
-
eSigning capabilities for quick approvals.
-
Cloud storage for secure document management.
Users can be assured of their data safety, as pdfFiller implements robust security measures to protect sensitive information.
After Submission: What Happens Next?
Once the form is submitted, the processing begins, and beneficiaries can track the status of their submission. It’s important to stay vigilant for any follow-up actions that may be required and to keep abreast of expected timelines for processing.
Privacy and Security in Handling Your Form Data
Data protection is of utmost importance, particularly pertaining to sensitive information contained in the form. pdfFiller adheres to strict regulations such as HIPAA and GDPR to ensure the security of user data. Users can trust that robust security measures are in place to safeguard their documents throughout the completion and submission process.
How to fill out the HI DHS 1179A
-
1.Access pdfFiller and search for the 'Hawaii Medicaid Change of Circumstance Report Form' using the search bar.
-
2.Once the form loads, familiarize yourself with the layout, noting the blank fields and checkboxes for various information.
-
3.Before you start filling out the form, gather necessary documents such as your Social Security Number (SSN), Client ID, and details of any changes in household members or income.
-
4.Begin by entering the primary individual's full name in the designated field as specified, including last name, first name, and middle initial.
-
5.Fill in the date of birth by selecting the correct date format from the calendar tool provided or entering it manually as mm/dd/yyyy.
-
6.Provide your Client ID or SSN in the appropriate section for identification purposes.
-
7.Fill out your current address and phone number in the fields provided, ensuring accuracy to avoid delays in processing.
-
8.Complete the sections detailing changes in household members, income, pregnancy status, and any third-party liability coverage as applicable.
-
9.Once all sections are filled, carefully review your entries for any errors or missing information.
-
10.After confirming that all details are accurate, add your signature in the designated signature field along with the date to validate your submission.
-
11.To save or download the completed form, click the 'Save' icon or choose 'Download' from the menu. You can also submit it digitally if that option is available.
-
12.Choose your preferred method for submission, whether via an online portal, mailing, or submitting in person, and follow any provided instructions.
Who is eligible to use the Hawaii Medicaid Change of Circumstance Report Form?
The form is intended for use by Medicaid beneficiaries residing in Hawaii and their authorized representatives, including legal guardians and conservators, to report important changes affecting their Medicaid eligibility.
What are the reporting deadlines for this form?
Beneficiaries must report changes within 15 days of the event. Failure to do so may result in benefits being denied or terminated, making timely submission critical.
How do I submit the Hawaii Medicaid Change of Circumstance Report Form?
You can submit the form through multiple methods: directly online via the Medicaid portal, mailing it to your local Department of Human Services office, or delivering it in person.
What supporting documents are required with the form?
While not always required, it’s helpful to include documentation that supports your reported changes, such as proof of income, residency, and any relevant employment information.
What are common mistakes to avoid when filling out this form?
Common errors include omitting key information, misreporting SSNs or client IDs, and failing to sign the form. Ensure that all sections are thoroughly completed to prevent delays.
How long does it take to process the changes reported via this form?
Processing times can vary, but generally, changes reported are assessed within 30 days. Check with your local office for specific timelines and potential factors that might affect processing.
What happens if I do not report a change in circumstances?
Not reporting changes like income or household size can lead to penalties, including the denial or termination of Medicaid benefits. It is crucial to report any changes promptly.
Related Forms








Related Catalogs
Get the latest insights from our blog



If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.