
Last updated on
Nov 9, 2026

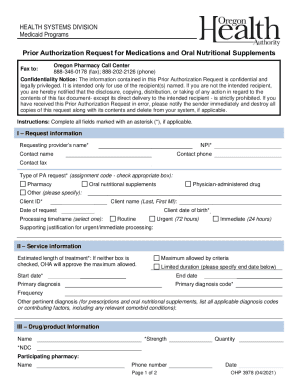
OR CareOregon Pharmacy Provider Reconsideration Request Form 2016 free printable template
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is OR CareOregon Pharmacy Provider Reconsideration Request Form
The Pharmacy Provider Reconsideration Request Form is a healthcare document used by providers in Oregon to appeal a denial of medication coverage for Oregon Health Plan members.
pdfFiller scores top ratings on review platforms




Who needs OR CareOregon Pharmacy Provider Reconsideration Request Form?
Explore how professionals across industries use pdfFiller.

OR CareOregon Pharmacy Provider Reconsideration Request Form is needed by:
-
Healthcare providers in Oregon
-
Pharmacists handling medication claims
-
Medical billing professionals
-
Insurance coordinators for health plans
-
Patients seeking medication coverage
-
Attorneys specializing in health law
Comprehensive Guide to OR CareOregon Pharmacy Provider Reconsideration Request Form
What is the Pharmacy Provider Reconsideration Request Form?
The Pharmacy Provider Reconsideration Request Form serves a crucial function in appealing medication denials for Oregon Health Plan members. This form facilitates healthcare providers in their efforts to ensure patients receive the medications they need. Key components of this form include essential patient specifics, prescriber details, and documentation of the medication denial.
Utilizing this pharmacy reconsideration form can significantly improve the chances of successful medication coverage appeals. Detailed sections ensure that all necessary aspects are addressed, allowing for a comprehensive request.
Purpose and Benefits of the Pharmacy Provider Reconsideration Request Form
This form plays a vital role in the healthcare process by helping providers secure necessary medication for patients under the Oregon Health Plan. With its structured approach, it assists in ensuring that patients receive timely medication coverage, thereby promoting better health outcomes.
The Pharmacy Provider Reconsideration Request Form aids in clarifying reasons for denial and provides a platform to address any issues with the initial application. This is paramount for maintaining access to prescriptions that are critical for patient care.
Eligibility Criteria for the Pharmacy Provider Reconsideration Request Form
Eligibility to file the Pharmacy Provider Reconsideration Request Form primarily includes prescribers and healthcare providers who are involved in patient care under Oregon's Health Plan. It's essential to meet specific criteria, such as being a resident of Oregon and providing valid patient information.
-
Prescribers must provide signed authorization.
-
Healthcare providers should have legitimate cases for appeals.
-
Patients must be enrolled in the Oregon Health Plan.
How to Fill Out the Pharmacy Provider Reconsideration Request Form Online (Step-by-Step)
Filling out the Pharmacy Provider Reconsideration Request Form requires attention to detail. Begin by accessing the online form and entering the required fields step by step, ensuring that all information is accurate.
-
Provide the patient’s full name.
-
Enter the date of birth in the designated format.
-
Include the Member ID carefully.
-
Obtain and add the prescriber’s signature.
Following these steps carefully helps ensure accuracy and completeness during submission, which is critical for a successful appeal.
Required Documents and Supporting Materials
When submitting the Pharmacy Provider Reconsideration Request Form, it's important to include the necessary supporting documentation. This may bolster your appeal and provide additional evidence of the medication’s necessity.
-
Prior authorization documents.
-
Clinical notes outlining patient history.
-
Pharmacy records demonstrating previous prescriptions.
Thoroughness in including these materials can significantly influence the success of the reconsideration process.
When to Submit the Pharmacy Provider Reconsideration Request Form
Timeliness is crucial when submitting the Pharmacy Provider Reconsideration Request Form. It is important to adhere to the 60-day submission requirement from the date of medication denial notification. Late submissions can result in the dismissal of your request.
-
Submit promptly to avoid complications.
-
Be aware of the specific deadline related to the denial date.
Prompt submission of the form can lead to quicker resolutions and access to necessary medication, benefiting patient care.
Submission Methods and Delivery of the Pharmacy Provider Reconsideration Request Form
Providers can submit the completed Pharmacy Provider Reconsideration Request Form through various channels, including fax, online submission, or mailing. Each method has its considerations that must be taken into account to ensure the form is delivered correctly.
-
Faxing the form to the designated number.
-
Using the online platform for submission.
-
Mailing to the appropriate address with tracking options.
What Happens After You Submit the Form?
After submitting the Pharmacy Provider Reconsideration Request Form, the review and processing of the appeal will begin. Timelines for reviews may vary, but healthcare providers can follow up on the status to track the appeal’s progress.
If amendments or corrections are needed, understanding the process for adjusting the form is crucial to ensure that all details are accurate and current.
Importance of Security and Compliance when Handling the Pharmacy Provider Reconsideration Request Form
Handling sensitive information via the Pharmacy Provider Reconsideration Request Form requires strict adherence to security and compliance measures. Solutions like pdfFiller provide encryption and are compliant with HIPAA and GDPR regulations to protect patient data.
Providers can be confident in the privacy of patient information when utilizing secure document handling practices while filling out or submitting the form.
Elevate Your Pharmacy Provider Reconsideration Process with pdfFiller
Enhance the Pharmacy Provider Reconsideration Process by utilizing pdfFiller for an efficient and secure form-filling experience. The platform allows for easy online access and supports features such as eSigning and document sharing, simplifying the overall process.
By leveraging such tools, healthcare providers can improve their workflow, ensuring that submissions are completed thoroughly and accurately.
How to fill out the OR CareOregon Pharmacy Provider Reconsideration Request Form
-
1.Access the Pharmacy Provider Reconsideration Request Form on pdfFiller by searching for its name or using a direct link to the form. Ensure you are logged in to your account.
-
2.Once the form is opened, familiarize yourself with the fillable fields. These fields typically include Patient Name, Date of Birth, and Member ID.
-
3.Before filling out the form, gather all necessary information such as the patient's identification details, the specific medication denial reasons, and any supporting documentation.
-
4.Begin completing the form by entering the patient's details into the designated fields. Make sure to provide accurate and complete information to avoid delays.
-
5.After filling in all required information, review each section of the form carefully to ensure no fields are left incomplete or contain errors.
-
6.Use pdfFiller's features to highlight or add notes for any additional information or supporting documents that may accompany the submission.
-
7.Once you are confident the form is complete and accurate, finalize the document by saving it within pdfFiller.
-
8.To submit the form, you can choose to download it directly or use the submission features available within pdfFiller. Ensure all files are properly formatted as required before sending.
Who is eligible to use the Pharmacy Provider Reconsideration Request Form?
Eligibility to use this form typically includes healthcare providers working with Oregon Health Plan members who have faced a medication coverage denial.
What is the deadline for submitting the reconsideration request?
The form must be submitted within 60 days of receiving the initial denial notice to ensure the appeal is considered valid.
How do I submit the Pharmacy Provider Reconsideration Request Form?
The form can be submitted by faxing it to the appropriate Oregon Health Plan office or through electronic submission methods allowed by your healthcare facility.
What supporting documents are required with this form?
You should include supporting documentation such as any previous approvals, denial letters, and clinical notes that substantiate the need for the medication being requested.
What common mistakes should I avoid when filling out the form?
Common mistakes include leaving fields blank, providing incorrect member IDs, and failing to attach all required supporting documents. Double-check all entries before submission.
How long does it take to process the reconsideration request?
Processing times can vary but typically range from several weeks to a few months, depending on the complexity of the case and the volume of submissions.
What should I do if I have questions about the form after submission?
If you have questions after submission, contact the Oregon Health Plan customer service or the department handling your appeal for further information or clarification on your case.
OR CareOregon Pharmacy Provider Reconsideration Request Form Form Versions
Related Forms







Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.