
Last updated on Jul 1, 2026

Get the free Infertility Medication Request Form
We are not affiliated with any brand or entity on this form
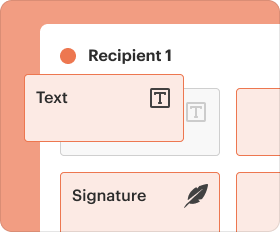
Fill out
Complete the form online in a simple drag-and-drop editor.
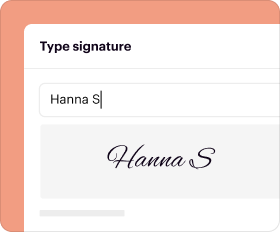
eSign
Add your legally binding signature or send the form for signing.
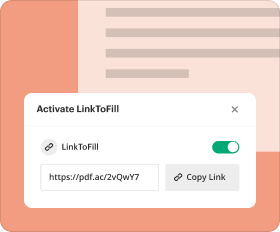
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Infertility Medication Request Form
The Infertility Medication Request Form is a medical document used by healthcare providers to request infertility medications from Aetna Specialty Pharmacy.
pdfFiller scores top ratings on review platforms




Who needs Infertility Medication Request Form?
Explore how professionals across industries use pdfFiller.

Infertility Medication Request Form is needed by:
-
Physicians prescribing infertility medications
-
Patients seeking infertility treatment
-
Insurance coordinators handling claims
-
Pharmacists fulfilling specialty prescriptions
-
Healthcare administrative staff managing medical records
Comprehensive Guide to Infertility Medication Request Form
What is the Infertility Medication Request Form?
The Infertility Medication Request Form is a crucial document for individuals seeking infertility treatments. This form enables patients to request necessary medications from Aetna Specialty Pharmacy, ensuring a smoother process in accessing treatments. Completing this form is vital as it serves as the primary means to obtain infertility medications, facilitating the overall treatment journey.
Purpose and Benefits of the Infertility Medication Request Form
This form is essential for a variety of reasons, providing multiple benefits for both patients and healthcare providers. Key advantages include:
-
Streamlined medication requests, ensuring timely treatment for patients.
-
Accurate information submission, which is critical for efficient processing.
-
Facilitation of insurance verification, helping avoid unexpected costs.
Overall, the Infertility Medication Request Form enhances the prescribing and medication acquisition process, making it easier for all involved parties.
Key Features of the Infertility Medication Request Form
The Infertility Medication Request Form includes several essential components that must be filled out correctly:
-
Patient information, ensuring clarity on who is making the request.
-
Diagnosis codes, which are critical for insurance and treatment accuracy.
-
A prescriber’s signature that confirms the authenticity and legal requirement.
-
Details regarding the medications requested, including quantities and specific prescriptions.
Each section is designed to capture important information that plays a significant role in the treatment process.
Who Needs the Infertility Medication Request Form?
The Infertility Medication Request Form should be completed by various individuals:
-
Patients undergoing infertility treatments needing specific medications.
-
Physicians who are prescribing treatments that require insurance verification.
-
Individuals meeting eligibility criteria dictated by their insurance providers.
Understanding who is required to fill out this form is vital for ensuring proper medication acquisition.
How to Fill Out the Infertility Medication Request Form Online (Step-by-Step)
Filling out the Infertility Medication Request Form electronically is a straightforward process. Follow these steps to ensure accuracy:
-
Access the form via pdfFiller, using a web browser of your choice.
-
Complete each fillable field carefully, providing accurate patient and physician information.
-
Double-check diagnosis codes and other medical details to avoid errors.
-
Obtain the required prescriber’s signature before submitting the form.
-
Review the completed form for clarity and accuracy before final submission.
Submission Methods and Delivery for the Infertility Medication Request Form
Proper submission of the completed Infertility Medication Request Form is crucial. Here are the available methods:
-
Online submission through platforms like pdfFiller.
-
Faxing to the designated pharmacy or healthcare provider.
-
Review any deadlines to prevent delays in medication processing.
Additionally, confirm receipt to ensure the form was successfully submitted and track the medications ordered.
Information Security and Compliance for the Infertility Medication Request Form
Handling sensitive information within the Infertility Medication Request Form requires strict adherence to security measures:
-
Implementation of privacy safeguards to protect personal data.
-
Compliance with regulations such as HIPAA and GDPR.
-
Utilization of pdfFiller’s security features ensuring document safety.
The importance of secure data handling cannot be overstated, ensuring both privacy and compliance are maintained.
Common Errors and How to Avoid Them When Completing the Form
Common mistakes can occur while filling out the Infertility Medication Request Form, including:
-
Omitting necessary fields leading to incomplete submissions.
-
Entering incorrect diagnosis codes, which can delay treatment.
-
Not securing the prescriber’s signature, which is mandatory.
To avoid these issues, consider reviewing the form thoroughly or consulting a healthcare professional if uncertainties arise.
The Path Ahead After Submitting the Infertility Medication Request Form
Once the Infertility Medication Request Form is submitted, users can expect:
-
Tracking the status of their submission to stay informed.
-
Addressing potential rejections or requests for additional information promptly.
-
Guidance through the renewal or resubmission process if necessary.
Being prepared for these next steps is essential for successful medication acquisition.
Transform Your Infertility Medication Request Process with pdfFiller
Utilizing pdfFiller can significantly enhance the experience of completing the Infertility Medication Request Form. Key benefits include:
-
Seamless editing and eSigning capabilities for quick modifications.
-
User-friendly interface for efficient form management.
-
Secure sharing features that protect sensitive healthcare documents.
Consider using pdfFiller to simplify your infertility medication request process and meet all your form-filling needs efficiently.
How to fill out the Infertility Medication Request Form
-
1.Access the Infertility Medication Request Form on pdfFiller by searching for the form name in the platform's search bar.
-
2.Once located, click on the form to open it in the pdfFiller editor interface.
-
3.Before filling out the form, gather necessary information such as patient details, insurance information, and specific medication requirements.
-
4.Begin entering information in the required fields, using the fillable fields labeled clearly, such as 'First Name:' and 'Last Name:'.
-
5.Continue to fill in the 'DOB:', 'Address:', 'Phone:', 'Weight:', 'Height:' and 'Allergies:' sections with accurate details.
-
6.Input the insurer’s details, including 'Carrier Name:', 'Member ID #:', 'Group #:', and check boxes for Medicare or Medicaid if applicable.
-
7.Move to the diagnosis sections and fill in 'Primary ICD Code:' and 'Other ICD code:' as necessary, ensuring you have accurate codes.
-
8.In the 'Prescription' section, detail the specific medication and quantities required for treatment.
-
9.Ensure you complete the 'Prescriber’s Signature (Required by Law)' field. This is essential for legal compliance.
-
10.Review all the entries to verify that all required fields are filled correctly and no information is missing.
-
11.Once satisfied, you can save your work to your pdfFiller account or download a copy to your device for submission.
-
12.To submit the form, follow any additional instructions from Aetna Specialty Pharmacy or relevant parties regarding how to send the completed form.
Who needs to fill out the Infertility Medication Request Form?
The form must be completed by physicians prescribing infertility medications on behalf of their patients. Patients may also need to provide supporting information, but ultimately, it is the physician who signs and submits the request.
Are there any specific eligibility requirements for submitting this form?
Typically, eligibility requirements include being an active patient covered by Aetna insurance. It's important to have your insurance details ready to ensure coverage for the requested medications.
What is the process for submitting the Infertility Medication Request Form?
After completing the form, you must submit it directly to Aetna Specialty Pharmacy. Typically, this can be done electronically via email or through their online submission portal, depending on the latest guidelines.
What supporting documents are required when submitting the form?
Along with the form, you may need to provide proof of patient's insurance coverage and clinical notes from the physician that justify the request for infertility medications.
What common mistakes should I avoid when completing the form?
Make sure all required fields are filled out completely and accurately. Failing to provide a prescriber's signature or missing medication details are common errors that can delay processing.
How long does it take for the form to be processed?
Processing times can vary, but typically, you can expect a response from Aetna Specialty Pharmacy within a few business days. Always check for specific timelines if the request is urgent.
Can I edit the Infertility Medication Request Form after signing?
Once the form is signed, it should not be altered. If changes are needed, it is advised to void the current form and complete a new one to maintain legal compliance.
Related Content
Related Forms





If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.