
Last updated on
Oct 31, 2026

PA WellSpan Health Form 2606 2015 free printable template
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is PA WellSpan Health Form 2606
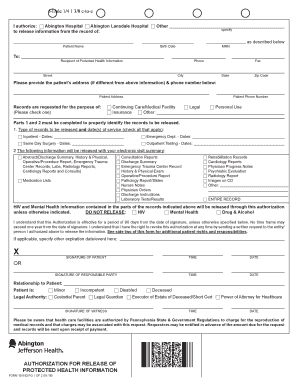
The Authorization to Use or Disclose Health Information is a healthcare form used by patients in Pennsylvania to permit the release of their medical records.
pdfFiller scores top ratings on review platforms




Who needs PA WellSpan Health Form 2606?
Explore how professionals across industries use pdfFiller.

PA WellSpan Health Form 2606 is needed by:
-
Patients seeking to disclose their medical information
-
Representatives acting on behalf of a patient
-
Witnesses verifying the patient's consent
-
Healthcare providers needing authorization to share records
-
Medical facilities requiring patient consent for treatment
Comprehensive Guide to PA WellSpan Health Form 2606
What is the Authorization to Use or Disclose Health Information?
The Authorization to Use or Disclose Health Information is a crucial form in Pennsylvania's healthcare sector. It is designed to grant permission for healthcare providers to release patient medical records. Understanding the key terminology associated with this authorization is essential, as it directly relates to patient rights and privacy.
Key terms include 'health information,' which refers to any medically related information that is maintained by healthcare entities, and 'authorization,' which signifies a patient’s consent for their information to be disclosed. The importance of this form cannot be understated; it ensures that patients exert control over their personal health information.
Purpose and Benefits of the Form
This authorization form facilitates the exchange of health information between patients and providers, streamlining access to medical records. Patients can easily authorize their healthcare representatives to obtain necessary information, paving the way for informed decision-making in their care.
Benefits extend to both patients and their representatives. By employing a health information release form, patients can authorize the release of their medical history efficiently, which is particularly beneficial during emergencies or transitions in care. Additionally, it enhances communication among healthcare professionals, ultimately leading to improved patient outcomes.
Key Features of the Authorization to Use or Disclose Health Information
The authorization form includes several essential components that ensure clarity and ease of completion. First, it contains fillable fields where users input critical details, such as the 'Patient Name' and 'Date of Birth.' There are also checkboxes available for different types of data disclosure.
Moreover, if a patient is unable to sign, the form provides options for a witness to sign on their behalf, ensuring that consent is still formally obtained. This feature is particularly important in circumstances where patients may be incapacitated.
Who Needs the Authorization to Use or Disclose Health Information?
The need for the Authorization form extends to several roles, including Patients, Representatives, and Witnesses. Each of these individuals plays a vital role in ensuring that health information is shared legally and ethically.
Circumstances that necessitate the use of this form include when patients wish to share their medical history with a secondary party, such as a family member or another healthcare provider. Ultimately, this form is crucial in safeguarding patient rights while facilitating necessary communication among involved parties.
Eligibility Criteria and State-Specific Rules
Eligibility to complete the Authorization form often requires certain considerations based on age or specific medical conditions. In Pennsylvania, specific legal criteria govern who can sign this authorization, especially concerning minors or individuals deemed incapacitated.
Those completing the form must understand their state's legal provisions, including provisions relating to the HIPAA authorization form, which protects the privacy and handling of health information.
How to Fill Out the Authorization to Use or Disclose Health Information Online (Step-by-Step)
Filling out the Authorization to Use or Disclose Health Information is straightforward when following these steps:
-
Access the form via pdfFiller.
-
Enter the 'Patient Name' in the designated fillable field.
-
Input the 'Date of Birth' to verify patient identity.
-
Complete the address section as required.
-
Sign the form, ensuring all necessary fields are filled out.
-
If applicable, have a witness sign the form if the patient cannot.
These steps ensure that users effectively complete the form, making the process of obtaining health information more efficient.
Common Errors and How to Avoid Them
When completing the Authorization form, patients often make common mistakes that can lead to delays or rejected submissions. These errors include failing to complete all required fields or neglecting to sign and date the form accurately.
To avoid these common pitfalls, consider the following tips:
-
Double-check all fillable fields after completion.
-
Ensure that all signatures are obtained where necessary.
-
Verify that the form is submitted within any specified deadlines.
Attention to detail in these areas can significantly enhance the form's effectiveness.
How to Submit and Where to Deliver the Completed Form
Submitting the Authorization form can typically be done through multiple methods. Patients have the option to deliver the completed form via email or in-person at their healthcare provider's office.
It is essential to be aware of any associated fees, submission deadlines, or processing times that may apply. This can vary based on the healthcare facility's policies, making it crucial to clarify such details before submission.
Security and Compliance for the Authorization to Use or Disclose Health Information
In handling sensitive health information, security and privacy are paramount. The Authorization form incorporates necessary security measures to ensure that all patient data is managed in compliance with HIPAA and GDPR regulations.
pdfFiller employs advanced security protocols, including 256-bit encryption to protect user information, ensuring that the completion and submission of the Form maintains patient confidentiality at all times.
Experience Easy Form Completion with pdfFiller
Using pdfFiller's platform makes completing the Authorization form efficient and secure. The user-friendly interface simplifies the process of filling out the form, allowing patients to navigate easily through the required fields.
Unique features offered by pdfFiller include the ability to create fillable forms and eSign documents, enhancing the overall user experience when managing health information forms.
How to fill out the PA WellSpan Health Form 2606
-
1.To access the Authorization to Use or Disclose Health Information form on pdfFiller, navigate to the website and search for the form by name or use the appropriate link.
-
2.Once the form is open, familiarize yourself with the layout. Use pdfFiller’s tools to fill in your information in the designated fields, ensuring accuracy.
-
3.Before completing the form, gather essential information such as your full name, date of birth, address, and the specifics of the medical records you wish to disclose.
-
4.Carefully fill out each field according to the instructions, paying attention to any checkboxes or specific requirements for signatures.
-
5.Review all your entries for completeness and accuracy. Ensure that any required witness signatures are obtained if you are unable to sign the form yourself.
-
6.Once everything is filled in correctly, finalize the form by using the save function. You can review or make additional changes if necessary before saving.
-
7.After finalization, download the completed form or submit it directly through pdfFiller if required. Keep a copy for your records.
Who is eligible to use the Authorization to Use or Disclose Health Information form?
Patients in Pennsylvania seeking to authorize the release of their medical records, along with their representatives and witnesses, are eligible to use this form.
What is the purpose of the Authorization to Use or Disclose Health Information?
The form allows patients to give consent for the release of their medical information, specifying what information can be shared, with whom, and for what purpose.
How can I submit the completed Authorization form?
You can submit the completed form by downloading it and providing it to your healthcare provider or medical facility as required.
What supporting documents are needed when using this form?
Typically, no additional documents are required, but you may need to provide identification or proof of representation if acting on behalf of another person.
Are there any deadlines to submit the Authorization to Use or Disclose Health Information?
While there are no specific deadlines for the form itself, it should be submitted promptly to ensure timely medical care and information sharing as needed.
What common mistakes should I avoid when filling out the form?
Ensure all required fields are filled out completely, check the accuracy of your personal information, and verify that all necessary signatures are obtained.
How long does it take to process the Authorization form?
Processing times may vary by healthcare provider but generally should not take more than a few days once the form is submitted.
PA WellSpan Health Form 2606 Form Versions
Related Forms









Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.