
Last updated on
Jul 2, 2026

Get the free Florida Health Information Disclosure Authorization
We are not affiliated with any brand or entity on this form
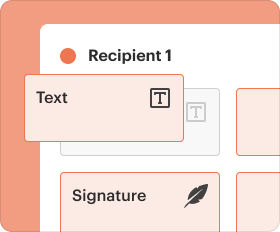
Fill out
Complete the form online in a simple drag-and-drop editor.
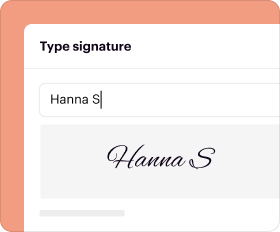
eSign
Add your legally binding signature or send the form for signing.
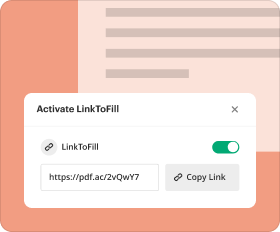
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is FL Health Info Release
The Florida Health Information Disclosure Authorization is a medical records release form used by patients to authorize the release of their health information to specific individuals or organizations.
pdfFiller scores top ratings on review platforms




It was easy once I got the hang of it
It was easy once I got the hang of it. It is a time saver. LOVED IT.
Good product
N. Rages
Easy to use and good for business
Easy to use and easy to get support.
Love this Program
Love this Program. I have an insurance business and it work wonderful with my customer.
Great price and works for what I needed.
Who needs FL Health Info Release?
Explore how professionals across industries use pdfFiller.

FL Health Info Release is needed by:
-
Patients seeking to share their medical records
-
Healthcare providers requiring patient consent
-
Legal representatives of patients
-
Insurance companies for claims processing
-
Family members requesting access to health information
Comprehensive Guide to FL Health Info Release
What is the Florida Health Information Disclosure Authorization?
The Florida Health Information Disclosure Authorization is a critical form used to allow the release of a patient’s health information to designated individuals or organizations. This form plays a vital role in the healthcare process, ensuring that sensitive health information is shared only with authorized recipients. Health information that can be disclosed includes medical history, treatment records, and other relevant health data.
Understanding the details of the health information disclosure form helps patients manage their health information effectively, empowering them to make informed decisions about their care.
Purpose and Benefits of the Florida Health Information Disclosure Authorization
The primary purpose of the Florida Health Information Disclosure Authorization is to provide a legal framework for patients to authorize access to their medical records. Patients require this authorization form for various reasons, including the need for medical consultations, second opinions, or rehabilitation services.
Benefits of this form extend to all parties involved:
-
Patients can ensure that their health information is shared securely with trusted healthcare providers.
-
Healthcare providers can access necessary information to deliver comprehensive care responsibly.
-
Third parties can obtain relevant health details to assist in different legal or insurance matters.
Key Features of the Florida Health Information Disclosure Authorization
This form includes essential elements such as patient information, recipient details, and the specific health information being released. It features fillable fields for easy completion and checkboxes to indicate consent for various types of disclosures.
-
Patient’s full name and contact information.
-
Names and addresses of recipients.
-
Types of health information being disclosed, such as test results and treatment history.
-
Expiration date of the authorization.
-
Signature area for the patient or legal representative.
Who Should Use the Florida Health Information Disclosure Authorization?
The Florida Health Information Disclosure Authorization should be completed by any patient who wishes to share their health information. This form is also relevant for legal representatives acting on behalf of patients who are unable to sign due to age or health concern.
Legal representatives must ensure they have the proper authority to sign on the patient's behalf, complying with applicable laws governing such actions.
How to Fill Out the Florida Health Information Disclosure Authorization Online (Step-by-Step)
Filling out the Florida Health Information Disclosure Authorization online is straightforward using the pdfFiller platform. Follow these steps:
-
Access the Florida Health Information Disclosure Authorization form on pdfFiller.
-
Enter your personal information in the designated fields.
-
Provide details about the recipient and the specific information being released.
-
Use checkboxes for selecting consent and specify the duration of the authorization.
-
eSign the form electronically and save a copy for your records.
Common Errors and How to Avoid Them When Completing the Form
When filling out the Florida Health Information Disclosure Authorization, users often encounter common mistakes, which include incomplete information or unclear consent. To ensure accuracy, follow these tips:
-
Double-check all entered information before submission.
-
Be specific about what information you are authorizing for release.
-
Ensure all signatures are collected where required.
-
Keep a copy of the completed form for your own records.
Submission Methods for the Florida Health Information Disclosure Authorization
Once the Florida Health Information Disclosure Authorization is completed, it must be submitted to the appropriate healthcare provider or organization as required. Common submission methods include:
-
Mailing the form to the recipient's address.
-
Submitting it in person at the healthcare provider's office.
-
Using electronic submission portals if available.
Be aware of any submission fees, deadlines, or processing times that may be applicable.
What Happens After Submission of the Florida Health Information Disclosure Authorization?
After submitting the Florida Health Information Disclosure Authorization, you can expect to receive confirmation of receipt from the healthcare provider. It is advisable to track the status of your authorization request. If any changes are needed, you may need to complete a new authorization form.
Security and Compliance of the Florida Health Information Disclosure Authorization
The security of personal health information is paramount. The Florida Health Information Disclosure Authorization complies with HIPAA and GDPR regulations to protect patient data. When handling sensitive health information, healthcare providers implement robust data protection measures to ensure confidentiality and integrity.
Make the Process Easier with pdfFiller
Utilizing pdfFiller for filling out the Florida Health Information Disclosure Authorization simplifies the process significantly. The platform provides various tools to edit, eSign, and manage your forms with ease, ensuring that users can complete and submit their authorizations efficiently.
How to fill out the FL Health Info Release
-
1.To start, visit pdfFiller and search for the Florida Health Information Disclosure Authorization form or use a direct link provided by your healthcare provider.
-
2.Once the form is open, familiarize yourself with the layout. The form contains multiple blank fields for your personal information, details about your healthcare provider, and the recipient of the information.
-
3.Before completing the form, gather necessary documents like your identification and the details of the person or organization receiving the health information.
-
4.Begin filling in your personal details at the top of the form. This typically includes your full name, address, and contact information.
-
5.Next, provide the name and contact details of your healthcare provider, as well as the specifics of the health information you are authorizing for release.
-
6.In the designated section, clearly specify the individuals or organizations you are allowing to receive your health information. This is crucial for ensuring your privacy is maintained.
-
7.Once all fields are completed, review each entry to ensure all information is accurate and complete to avoid processing delays.
-
8.After finalizing the form, use pdfFiller's features to sign the document electronically. You can usually find the signature option in the toolbar.
-
9.Finally, choose how you want to save or submit the form. You can download a copy for your records or send it directly to the designated recipient through pdfFiller’s submission options.
Who is eligible to complete the Florida Health Information Disclosure Authorization?
Any patient who wishes to authorize the release of their health information can fill out this form, including legal representatives acting on the patient’s behalf.
Are there any deadlines for submitting this authorization form?
While there is no specific deadline for submitting this form, it is advisable to complete and submit it as soon as possible to ensure timely access to your health information.
How should I submit the completed form?
You can submit the completed form via email, fax, or in-person delivery, depending on the requirements of the healthcare provider or organization receiving the authorization.
What documents do I need to accompany my authorization form?
You typically do not need additional documents to accompany the form, but having your ID and any relevant insurance information may be helpful.
What common mistakes should I avoid when completing this form?
Ensure all fields are accurately completed and double-check for any missing signatures. Also, avoid using vague descriptions when listing the information you wish to disclose.
How long does it take to process the authorization request?
Processing times can vary by organization, but generally, it may take a few days to a couple of weeks for them to process your request and provide the requested health information.
What do I do if I change my mind about the authorization?
You have the right to revoke your authorization at any time by submitting a written request to the healthcare provider or organization that holds your health information.
Related Forms






If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.