

Get the free Request for Redetermination of Medicare Prescription Drug Denial
We are not affiliated with any brand or entity on this form
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Medicare Drug Appeal
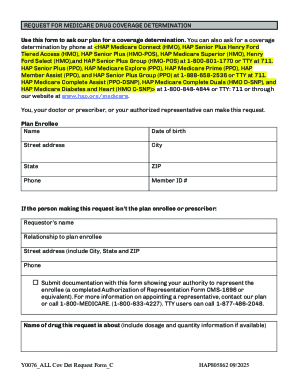
The Request for Redetermination of Medicare Prescription Drug Denial is a healthcare form used by enrollees to appeal a denial of coverage for a prescription drug.
pdfFiller scores top ratings on review platforms




Who needs Medicare Drug Appeal?
Explore how professionals across industries use pdfFiller.

Medicare Drug Appeal is needed by:
-
Medicare enrollees seeking to contest a drug denial
-
Family members of enrollees acting on their behalf
-
Healthcare providers submitting appeals for patients
-
Case managers and advocates aiding in the appeal process
-
Insurance representatives for necessary documentation
-
Legal professionals assisting clients with appeals
How to fill out the Medicare Drug Appeal
-
1.Access the Request for Redetermination of Medicare Prescription Drug Denial form on pdfFiller by visiting their website and using the search feature.
-
2.Open the form within the pdfFiller interface. Familiarize yourself with the available tools like text boxes, checkboxes, and signature fields.
-
3.Before starting, gather all necessary information including enrollee's name, date of birth, address, details about the denied prescription drug, prescriber's information, and any prior purchase confirmations.
-
4.Fill out each field clearly. Begin with the enrollee's personal information, then provide details of the prescription drug in question.
-
5.Use checkboxes where applicable to confirm purchases and consent. Be sure to include any additional information that may support your appeal.
-
6.Review all completed sections to ensure there are no omissions or errors. Double-check critical details such as drug names and prescription dates.
-
7.Finalize the form by signing it within the designated signature field to authenticate the request.
-
8.Once completed, save your progress through the pdfFiller interface by selecting the save option.
-
9.Download a copy of your filled form for your records. In the pdfFiller platform, choose the download option, ensuring you keep a secure copy.
-
10.Submit the form to the appropriate Medicare address as indicated on the denial notice. Follow any specific submission instructions provided for timely processing.
Who is eligible to use the Request for Redetermination form?
Medicare enrollees who have received a denial for coverage on a prescription drug are eligible to use the Request for Redetermination of Medicare Prescription Drug Denial form to appeal the decision.
What is the deadline for submitting this form?
You must complete and submit the Request for Redetermination form within 60 days from the date you receive your denial notice for your appeal to be considered.
How do I submit the Request for Redetermination form?
The completed Request for Redetermination form should be submitted directly to the Medicare plan's address provided in your denial notice. Ensure you follow any specific instructions included.
What supporting documents are required with this form?
Along with the Request for Redetermination form, you may need to provide supporting documents such as prescriptions, pharmacy receipts, and any correspondence regarding the denial to strengthen your appeal.
What are some common mistakes to avoid when filling out this form?
Common mistakes include leaving fields incomplete, failing to provide necessary supporting documentation, missing the submission deadline, and not including a signature. Carefully review all sections before submitting.
How long does it take to process the appeal after submission?
Processing times for appeals can vary but generally take up to 7 to 30 days. Keep an eye out for communication from your Medicare provider regarding the status of your appeal.
What should I do if my appeal is denied again?
If your appeal is denied, you have the right to request a further review through a hearing or review by an administrative law judge. It is advisable to seek assistance in preparing additional documentation to support your case.
Related Forms









Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.