
Last updated on
Oct 2, 2026

Boyette Orthopedics Patient Medical History Form free printable template
pdfFiller is not affiliated with any government organization
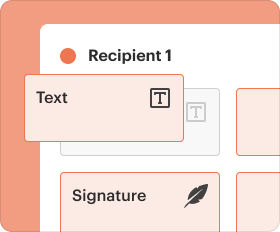
Fill out
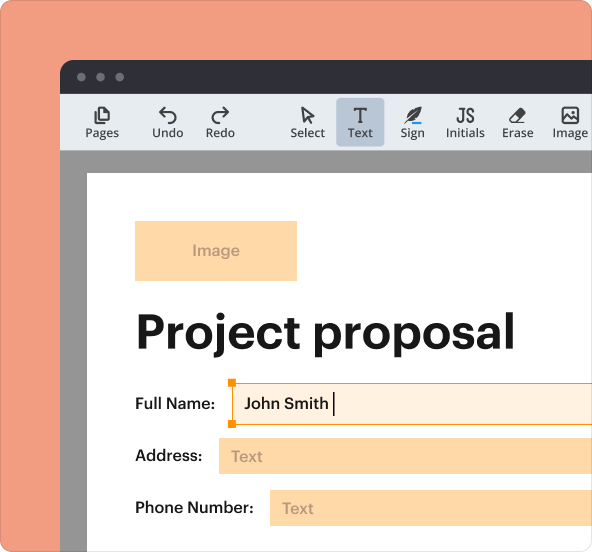
Complete the form online in a simple drag-and-drop editor.
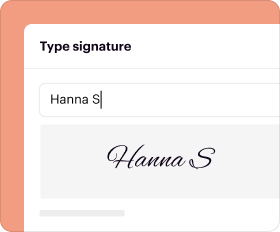
eSign
Add your legally binding signature or send the form for signing.
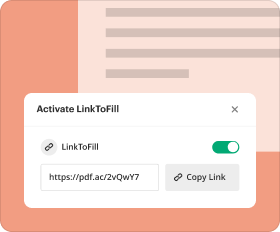
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Boyette Orthopedics Patient Medical History Form
The Patient Medical History Form is a medical document used by healthcare providers to collect essential medical information from patients for accurate diagnosis and treatment planning.
pdfFiller scores top ratings on review platforms




Who needs Boyette Orthopedics Patient Medical History Form?
Explore how professionals across industries use pdfFiller.

Boyette Orthopedics Patient Medical History Form is needed by:
-
Patients seeking medical care
-
Healthcare providers requiring medical history
-
Orthopedic specialists assessing patient condition
-
Administrative staff at medical facilities managing patient data
-
Insurance companies reviewing medical claims
Comprehensive Guide to Boyette Orthopedics Patient Medical History Form
What is the Patient Medical History Form?
The Patient Medical History Form serves a crucial role in collecting essential medical information from patients, enabling healthcare providers to deliver informed care. This healthcare intake form is pivotal in ensuring that medical professionals have comprehensive data to reference during consultations. With a complete medical history, practitioners can make more accurate assessments and treatment decisions, particularly during initial visits.
Purpose and Benefits of the Patient Medical History Form
Completing the medical history questionnaire offers significant advantages for both patients and healthcare providers. This form assists in shaping an effective diagnosis and treatment plan based on the patient's unique medical background. Providing accurate and complete information is vital for continuity of care, ensuring that all healthcare professionals involved in the patient’s treatment are well-informed.
Key Features of the Patient Medical History Form
The patient medical history form includes critical sections such as personal data, medical conditions, symptom reviews, medications, allergies, and more. Each section is designed with fillable fields, making it easier for patients to provide detailed information. Additionally, the form requires the patient’s signature to confirm the accuracy of the details provided, establishing trust and accountability in the patient-provider relationship.
Who Needs the Patient Medical History Form?
This form is typically required for new patients as well as returning patients who have updates to their health status. Various medical specialties utilize the patient registration form, with orthopedics being a prominent example. Maintaining a complete medical history is beneficial for all patients, facilitating more effective diagnosis and treatment across different healthcare scenarios.
How to Fill Out the Patient Medical History Form Online (Step-by-Step)
-
Login to your pdfFiller account.
-
Search for the patient medical history form template in the library.
-
Fill out relevant sections, ensuring to provide accurate details.
-
Review the completed form for any discrepancies or missing information.
-
Save your changes and prepare for submission.
Common Errors and How to Avoid Them
Many individuals make frequent mistakes when filling out their medical history questionnaire, which can lead to delays in care. To prevent issues, consider this checklist before submission:
-
Ensure all personal data is accurate and up to date.
-
Review medical conditions and allergies for completeness.
-
Check that signatures are present where required.
How to eSign the Patient Medical History Form with pdfFiller
Signing the form is essential for validating the information contained within. pdfFiller simplifies adding a digital signature, allowing you to streamline the process. Follow these steps to apply your eSignature:
-
Open the form in pdfFiller.
-
Select the signature feature within the toolbar.
-
Choose or create your digital signature.
-
Place the signature in the designated area and save your changes.
Where to Submit the Patient Medical History Form
Submitting the patient medical history form can be done through various methods, including in-person drop-off or faxing it to Boyette Orthopedics & Sports Medicine. Ensure that you follow any specific guidelines or procedures set by the practice to ensure proper handling of your information.
Privacy and Data Protection for Your Medical History Information
Using pdfFiller guarantees the security and compliance of your data, adhering to regulations such as HIPAA. The platform employs robust data protection practices and encryption standards, ensuring that sensitive information is handled securely throughout the process.
Maximize Your Experience with pdfFiller for the Patient Medical History Form
Users are encouraged to leverage pdfFiller’s capabilities for managing their forms efficiently. The platform offers features such as template creation, form editing, and the advantages of cloud storage. Should you have queries while completing the form, pdfFiller provides valuable support to assist you.
How to fill out the Boyette Orthopedics Patient Medical History Form
-
1.Access the Patient Medical History Form on pdfFiller by searching for it in the platform’s document library or using the provided link.
-
2.Once you have the form open, utilize the navigation tools to scroll through the document. Begin filling in the personal information fields such as 'Name' and 'Birthdate'.
-
3.Prepare the necessary medical information before starting the form. Gather details about your medical conditions, current medications, allergies, and any relevant family medical history.
-
4.Proceed to complete the sections on symptoms, medications, and past surgical history as prompted in the form. Make sure you provide accurate and detailed answers in the spaces provided.
-
5.Utilize checkboxes for sections where applicable; for example, in the allergies section, circle or mark all relevant allergies. Review each section carefully to ensure completeness.
-
6.Once you have filled in all necessary fields, review the document for accuracy to prevent any common mistakes like missing signatures or incorrect information entries.
-
7.Finally, save the filled form to your device or submit it via fax to Boyette Orthopedics & Sports Medicine as instructed. Download the form in your preferred format if needed.
Who needs to fill out the Patient Medical History Form?
The Patient Medical History Form is primarily for patients visiting healthcare providers, especially in orthopedic settings. It’s essential for any patient requiring medical assessment, surgery, or treatment.
What information do I need to gather before completing the form?
Before starting the Patient Medical History Form, gather your personal information, medical conditions, list of medications, allergies, and family health history. This will facilitate accurate completion.
How do I submit the form after filling it out?
You can submit the completed Patient Medical History Form via fax to Boyette Orthopedics & Sports Medicine or bring it with you to the appointment. Ensure it’s signed before submission.
What should I do if I made a mistake on the form?
If you noticed a mistake after submission, contact the healthcare provider’s office to correct it. It’s important for records to be accurate, especially regarding medical history.
Is there a deadline for submitting the Patient Medical History Form?
While there may not be a strict deadline, it is recommended to complete and submit the form before your scheduled healthcare appointment to ensure timely processing.
Does the Patient Medical History Form need notarization?
No, the Patient Medical History Form does not require notarization. You simply need to provide your signature in the appropriate section.
Where can I download a copy of the Patient Medical History Form?
You can download the Patient Medical History Form in PDF format from pdfFiller or other medical facilities’ websites that provide access to patient forms.
Related Content
Related Forms




Related Catalogs
Get the latest insights from our blog


If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.