
Last updated on
Aug 5, 2026

Zeeland Community Hospital ZCH-MS0345 2009-2026 free printable template
pdfFiller is not affiliated with any government organization
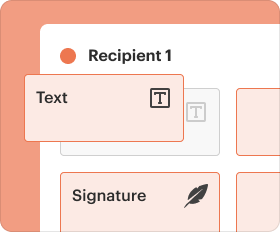
Fill out
Complete the form online in a simple drag-and-drop editor.
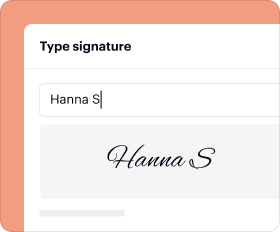
eSign
Add your legally binding signature or send the form for signing.
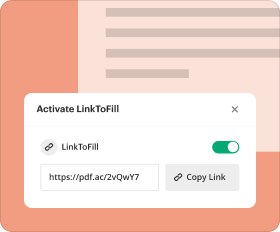
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Zeeland Community Hospital ZCH-MS0345
The Authorization for Release of Medical Information is a healthcare document used by patients to permit the release of their medical records from healthcare providers to designated recipients.
pdfFiller scores top ratings on review platforms




Who needs Zeeland Community Hospital ZCH-MS0345?
Explore how professionals across industries use pdfFiller.

Zeeland Community Hospital ZCH-MS0345 is needed by:
-
Patients requiring their medical records for personal use
-
Healthcare providers requesting patient information for treatment
-
Legal representatives managing a patient's healthcare decisions
-
Family members needing access to a loved one's medical information
-
Insurance companies requesting medical documentation for claims
Comprehensive Guide to Zeeland Community Hospital ZCH-MS0345
What is the Authorization for Release of Medical Information?
The Authorization for Release of Medical Information is a crucial form in healthcare, allowing patients to consent to the release of their medical records. This form emphasizes the significance of patient consent when accessing medical records, ensuring that sensitive information is shared appropriately. For patients at Zeeland Community Hospital and their associated physicians, this authorization is vital for proper communication and care.
Purpose and Benefits of the Authorization for Release of Medical Information
This authorization form serves multiple purposes for both patients and healthcare providers. It is necessary to ensure that medical records are shared securely and legally, promoting continuity of care. The benefits include improved communication among healthcare professionals, thus enhancing patient care. Additionally, patients maintain control over their own medical information, allowing them to decide who can access their records.
Key Features of the Authorization for Release of Medical Information
The form includes several key components that are essential for proper use. Required personal information fields consist of the patient's name, admission number, and dates of treatment. The form also includes specific fields such as 'Signature of Patient' and 'Witness Signature', ensuring compliance with confidentiality rules mandated by state and federal laws.
Who Needs the Authorization for Release of Medical Information?
This form is primarily needed by patients at Zeeland Community Hospital and their family members. It is required in scenarios where transfers between healthcare providers occur or when sharing information with specialists. Witnesses also play a crucial role, as their signatures validate the authenticity of the authorization.
How to Fill Out the Authorization for Release of Medical Information Online (Step-by-Step)
-
Access the form using pdfFiller.
-
Fill in all required personal information accurately.
-
Specify the treatment dates and type of medical information to be released.
-
Ensure the 'Signature of Patient' and 'Witness Signature' fields are completed.
-
Check the form for accuracy before submitting.
Submission Methods and Delivery
Patients have various options for submitting the completed Authorization for Release of Medical Information. They can submit it online through pdfFiller, in person at the healthcare facility, or via mail. It's essential to be aware of potential fees, deadlines, and expected processing times, as these can vary.
What Happens After You Submit the Authorization for Release of Medical Information
After submission, the review process begins, which typically involves verification of the form's accuracy and completeness. Patients can track the status of their submission and should be prepared to take action if the form is rejected, including making necessary corrections or re-submitting.
Security and Compliance for Handling the Authorization for Release of Medical Information
pdfFiller implements robust security features to ensure the safe handling of sensitive documents. These include strong encryption and adherence to HIPAA compliance standards. Participants should be conscious of privacy considerations when submitting their personal information to protect their medical records effectively.
How to Correct or Amend the Authorization for Release of Medical Information
In the event that corrections are needed after submission, specific steps should be followed. This process typically involves identifying the errors and then submitting an amended form with the correct information. Common reasons for amendments include changes in patient details or treatment dates, which must be handled promptly to maintain accurate medical records.
Experience the Ease of Completing Your Authorization for Release of Medical Information with pdfFiller
Utilizing pdfFiller makes the process of completing your authorization simple and efficient. The platform offers user-friendly features designed to streamline form filling and submission. Prioritizing the protection of sensitive information, pdfFiller ensures a secure experience for users managing their healthcare documentation.
How to fill out the Zeeland Community Hospital ZCH-MS0345
-
1.Begin by accessing pdfFiller and searching for 'Authorization for Release of Medical Information'.
-
2.Open the form, utilizing the fillable fields offered by the platform.
-
3.Gather required personal information including your name, admission number, and treatment dates before filling in the form.
-
4.Carefully complete each blank field, including specifying the type of medical information you wish to release and the purpose of disclosure.
-
5.Follow the instructions within the form, clicking the checkbox to affirm your understanding of the authorization process.
-
6.Once all fields are completed, review the document for any missing information or errors.
-
7.Seek assistance if you're uncertain about what to fill in any field to avoid mistakes.
-
8.After confirming all information is accurate, proceed to save or download the completed document.
-
9.You can then submit the form to the relevant healthcare provider or designated recipient as needed.
Who is eligible to complete this authorization form?
Any patient wishing to authorize the release of their medical information can complete this form. Both the patient and a witness must sign it to validate the request.
What is the processing time for this authorization?
Processing times can vary based on the healthcare provider's policy. Generally, it may take a few days to a week for the authorized medical information to be released once the form is submitted.
Are there any deadlines for submitting the authorization form?
It is advised to submit the authorization form as soon as possible, especially if the medical information is needed for upcoming appointments or legal requirements.
What supporting documents may be required with the form?
Typically, no additional documents are required. However, certain situations may necessitate proof of identity or legal authority, such as a power of attorney for signature.
How can I avoid common mistakes when filling out the form?
Ensure all sections are thoroughly filled out and double-check that both signatures—patient and witness—are included before submission. Carefully read all instructions and provide accurate information.
How is this form submitted once completed?
The completed form can be submitted directly to the healthcare provider or organization via mail, fax, or in-person drop-off based on their preferred submission methods.
What happens if the information expires before I can use it?
The authorization expires after six months unless specifically stated otherwise. If needed beyond this period, a new authorization form must be completed.
Related Content
Related Forms





Related Catalogs

If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.